What Is a Mixed Acid-Base Disturbance?
A combined acid base disturbance happens when more than one process is altering acid-base balance at the same point. Rather than a one simple picture, the blood shows indications of several overlapping disturbances. That is significant because a patient may appear acidotic, alkalotic, or even nearly normal on paper while still having a significant underlying problem.
The most common pairings involve metabolic acidosis along with a different process such as respiratory alkalosis. Clinically, this means one condition is decreasing bicarbonate or adding to acid load, while another is lowering carbon dioxide through hyperventilation. The result can be puzzling unless you use a systematic assessment approach and review the full clinical picture.
A combined acid–base imbalance is not just a lab finding. It often signals a significant metabolic abnormality, breathing compensation that is excessive or insufficient, or an additional problem affecting the lungs and kidneys at the same time. Because of that, test interpretation should always include serum chemistry, blood gas analysis, and the clinical context.
What Can an Elevated Anion Gap Signify?
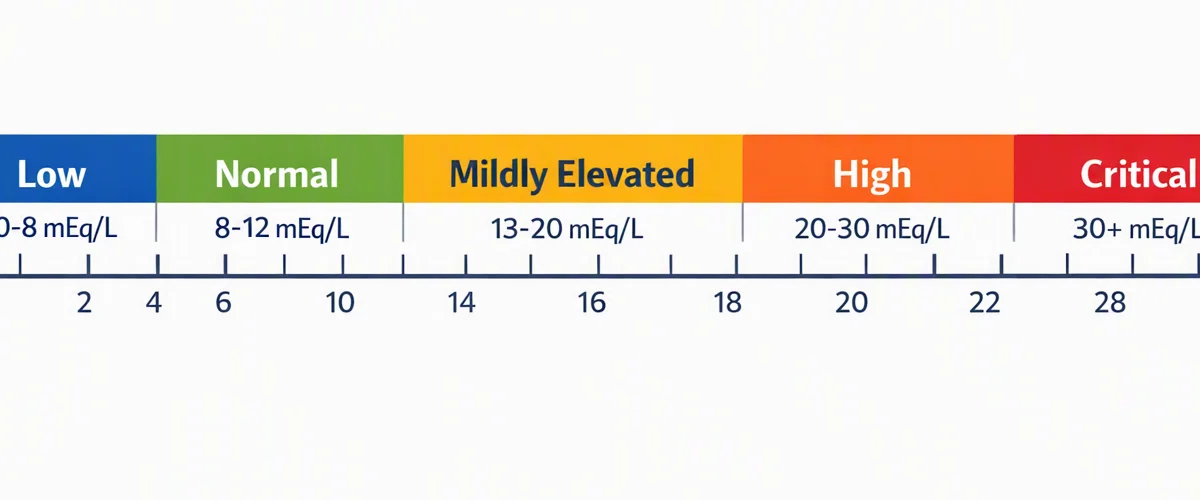
The anion gap is a computed value used to help identify imbalances in electrolytes and acid-base regulation. It shows the difference between measured cations and measured anions in the serum, and it offers a clue about the presence of unmeasured anions in the bloodstream. When the elevated anion gap is present, it usually suggests that extra acids are gathering.
An increased anion gap is most closely associated with high anion gap metabolic acidosis. In this pattern, bicarbonate is consumed while acids rise, leaving behind negatively charged byproducts that are not directly measured on a standard panel. These may come from lactic acid, ketones, toxins, or impaired renal clearance.
Understanding the anion gap helps refine the differential diagnosis. It does not tell you the exact cause by itself, but it strongly suggests that the body is dealing with a specific type of acid loading or loss of acid excretion. That is why the anion gap is such a useful part of laboratory interpretation.
How the Anion Gap Calculator Helps Interpretation
An Anion Gap Calculator streamlines the anion gap formula simpler to apply and helps reduce mistakes during quick assessment. The calculation typically uses serum sodium, serum chloride, and serum bicarbonate. Because these values are often already available on a basic metabolic panel, the calculator turns raw serum chemistry into a more clinically meaningful result.
The classic formula is: sodium medications causing low AG minus the sum of chloride and bicarbonate. That calculated value is the anion gap. A higher number supports the presence of extra unmeasured anions and raises concern for a high anion gap metabolic acidosis. The calculator can also help you spot whether the pattern suggests a single disorder or hints at a mixed acid-base disorder.
Using an Anion Gap Calculator is useful because the result alone is not enough. You still need to compare it with the blood gas, the pH, the pCO2, and the patient’s symptoms. In other words, the calculator supports clinical reasoning, but it does not replace it. The best use is as part of a broader diagnostic approach that includes compensation analysis and an underlying cause review.
Frequent Causes of Mixed Acid-Base Imbalances With Elevated Anion Gap
Various conditions can cause a mixed acid-base disorder with an high anion gap. Among the most common are lactic acidosis, ketoacidosis, and renal failure. Each one can create a elevated anion gap metabolic acidosis, and each can also occur along with another process such as alkalosis from breathing changes or respiratory compensation that is stronger than expected.
Lactic acidosis occurs when tissues are deprived of adequate oxygen or when cells cannot utilize oxygen normally. The result is excess lactate production and acid buildup. It is often seen in critical illness, poor perfusion, seizures, or major metabolic stress. If the patient is also ventilating rapidly, a respiratory alkalosis may occur simultaneously and make the pH less clearly abnormal.
Ketoacidosis happens when ketone production goes up, most often in uncontrolled diabetes, prolonged fasting, or alcohol-associated metabolic stress. The ketoacids raise the anion gap and decrease bicarbonate. If the person is respiring quickly from pain, anxiety, infection, or sepsis, the blood gas may show a second abnormality on top of the acidosis.
Renal failure can also cause retention of acids that are normally removed by the kidneys. As kidney function worsens, unseen acids accumulate and the serum anion gap may rise. This can happen slowly or rapidly, and it often requires careful attention to electrolyte patterns and the full serum chemistry profile.
Identifying Mixed Disorders from Laboratory Tests
The key to recognizing a mixed acid-base disorder is not just noticing an abnormal number. You need to interpret the arterial blood gas, including pH and pCO2, along with the chemistry panel. Together, these values indicate whether the body’s response is adequate or whether two separate processes are happening together.
The blood gas can show a low pH with low bicarbonate, which fits metabolic acidosis. But if the pCO2 is lower than expected, there may also be respiratory alkalosis. This is where the idea of a mixed disorder becomes important. The pH alone may not reveal the full story, especially if compensation is masking one component.
The delta gap is another useful concept. It compares the rise in anion gap with the fall in bicarbonate. If the changes do not match expected patterns, a mixed process may be present. For example, a very high anion gap with only mild bicarbonate reduction may suggest an additional metabolic alkalosis. Likewise, an unexpectedly low pCO2 may point to superimposed respiratory alkalosis rather than simple compensation.
In practical terms, abnormal labs should raise questions like: Is the pH acidemic or alkalemic? Is the pCO2 moving in the direction you would expect? Does the anion gap fit the degree of bicarbonate loss? This approach helps identify a straightforward pattern from a more complex metabolic disturbance.
Sequential Approach to Reading Outcomes
A systematic approach makes assessment much easier. First, review the pH to decide whether the patient is acidemic, too alkaline, or near normal. Then, establish whether the primary process appears metabolic or respiratory. After that, assess the serum anion gap to see whether there is evidence of increased anion gap metabolic acidosis. This stepwise method gives a reliable starting point for laboratory interpretation.
Then, use Winter's formula to predict the expected respiratory compensation for metabolic acidosis. If the measured pCO2 is well above than expected, there may be an additional respiratory acidosis. If the pCO2 is well below than expected, respiratory alkalosis may be present. That is one of the crucial steps in recognizing a mixed acid-base disorder.
In the end, assess whether the observed pattern fits the expected physiology. True compensation is the body’s normal response to a primary disorder, but compensation has boundaries. When the blood gas does not match the expected pattern, it indicates more than one process. That is often the hint that the patient has an underlying cause requiring urgent attention.
A useful rule: if the anion gap is elevated and the pCO2 does not match the expected compensatory response, think outside a single diagnosis and look for a second acid-base process.
Examples of Increased Anion Gap Mixed Disorders
A typical example is someone with sepsis who develops lactic acidosis. The underlying infection drives poor tissue perfusion and lactate buildup, causing high anion gap metabolic acidosis. Simultaneously, the patient may hyperventilate from fever, pain, or systemic stress, producing respiratory alkalosis. The blood gas can show a pH that is higher than expected because the two disorders partially offset each other.
Another case involves toxic alcohols. These substances can generate acids that raise the anion gap, leading to severe metabolic acidosis. If the patient is also breathing rapidly due to physiologic stress, agitation, or central nervous system effects, a mixed pattern may appear. The result is a serious diagnostic challenge that requires prompt recognition.
Salicylate poisoning is a classic mixed disorder. It often causes respiratory alkalosis early because the toxic exposure stimulates the respiratory center. Later, a high anion gap metabolic acidosis develops as acid metabolites accumulate. The combination can produce a deceptively near-normal pH, which is why blood gas analysis and serum chemistry must be reviewed together.
These patterns show why laboratory interpretation matters. A patient can be severely ill even when one number seems only mildly abnormal. The anion gap formula, pH, pCO2, and clinical presentation all need to be interpreted together to identify the correct diagnosis.
When to Obtain Prompt Medical Evaluation
Certain findings should warrant urgent medical evaluation, notably when they appear alongside an raised anion gap. Critical lab values such as a extremely low bicarbonate, severely abnormal pH, or extremely elevated serum anion gap may indicate a potentially fatal metabolic disturbance. These results need prompt clinical attention rather than routine follow-up.
Clinical signs matter just as much as lab results. Altered mental status, confusion, extreme weakness, rapid breathing, chest discomfort, or inability to stay awake can all signal a severe acid-base disorder. If the patient is not protecting the airway or cannot provide a reliable history, the urgency increases.
Shock is another important warning sign. Poor perfusion can worsen lactic acidosis and rapidly destabilize the acid-base status. In that setting, the elevated anion gap may reflect a serious underlying cause such as sepsis, toxic ingestion, or organ failure. Immediate evaluation is needed because these conditions can progress quickly.
In short, a mixed acid-base disorder with a high anion gap is not something to ignore. It can represent a dangerous electrolyte disorder or systemic illness that needs prompt diagnosis and treatment.
Frequently Asked Questions
What is considered an elevated anion gap?
An elevated anion gap is a increased result on an anion gap calculation using serum sodium, serum chloride, and serum bicarbonate. The exact cutoff can vary by laboratory because reference ranges differ, but a clearly increased value suggests excess unmeasured anions and raises concern for high anion gap metabolic acidosis. Always interpret the number with the rest of the blood gas and serum chemistry results.
How does a mixed acid-base disorder differ from a simple disorder?
A simple disorder has one primary acid-base problem with an appropriate compensatory response. A mixed acid-base disorder has two or more separate processes happening at the same time, such as metabolic acidosis plus respiratory alkalosis. The clue is often that the pH, pCO2, and bicarbonate do not fit the expected pattern for a single disorder.
Can a patient have both metabolic acidosis and respiratory alkalosis at the same time?
Certainly. This is a textbook mixed acid-base condition. It can happen in sepsis, salicylate poisoning, liver disease, or other conditions where the body is producing acid while also causing rapid breathing. In these cases, the pCO2 may be below the expected level for plain compensation, and the pH may appear less deranged than the severity of illness would suggest.
What conditions most commonly cause a high anion gap?
Common causes include lactic acidosis, ketoacidosis, renal failure, toxic alcohols, and salicylate poisoning. These conditions all create or retain acids that increase the anion gap. The best differential diagnosis comes from integrating the anion gap with the arterial blood gas, clinical findings, and other laboratory interpretation clues.
How do you calculate and interpret the anion gap in lab results?
The anion gap formula uses serum sodium minus the sum of serum chloride and serum bicarbonate. Anion Gap Calculator can make that process faster and help prevent calculation mistakes. Once you have the result, check it against the expected compensation using Winter's formula, review the pH and pCO2, and look for signs of a combined acid-base disorder. Interpretation works best when the calculated value is paired with the patient’s symptoms and underlying cause rather than assessed in isolation.