An anion gap calculator is a helpful diagnostic tool made to support interpret a blood chemistry panel or electrolyte panel. It combines serum sodium, chloride, and bicarbonate to produce a calculated value that aids clinical interpretation of acid-base balance. While the number itself is easy, the meaning behind it depends on the complete lab result, including albumin, the entire electrolytes, and the patient’s assessment.
This guide outlines how the anion gap works, how the anion gap formula incorporates sodium and related measurements, and why the result can point toward a particular metabolic disturbance such as metabolic acidosis or high anion gap metabolic acidosis. It also covers albumin correction, corrected anion gap use, reference range interpretation, and important diagnostic limitations.
How this Anion Gap Measures
The anion gap measures the difference between measured positive and negative charges in the blood. In plain language, it helps identify whether there are additional unmeasured ions in the bloodstream that may affect the body’s acid-base balance. Since the body keeps electrolytes in a narrow range, even small shifts in serum sodium, chloride, and bicarbonate can give useful indications.
Most clinicians use the anion gap as part of a broader serum chemistry review. It is not a standalone diagnosis. Instead, it is one piece of evidence that can guide the interpretation of a metabolic acidosis workup, especially when a patient has symptoms or other abnormal lab findings.
The idea behind the anion gap is that sodium is usually the main measured positive ion, while chloride and bicarbonate are two of the main measured negative ions. The gap reflects what is not directly measured. That is why the result can be useful when looking for hidden causes of a metabolic disturbance.
Anion Gap Formula
A standard anion gap formula is straightforward:
Anion gap = sodium - (chloride + bicarbonate)
Some tools may also include potassium, but most current references leave it out for ease. The main inputs are the sodium concentration, chloride level, and bicarbonate level. When these values are entered into an anion gap calculator, the tool gives a quick measurement that can be compared with the typical reference range.
For instance, if the sodium is 140, the chloride is 102, and the bicarbonate is 24, the calculation is:
140 - (102 + 24) = 14
That calculated value may fit within many commonly used normal limits, depending on the lab. Since ranges differ, the result should always be interpreted alongside the specific laboratory’s reported range and the overall clinical interpretation.
In use, the anion gap calculator is useful because it standardizes the interpretation of a routine blood chemistry panel. The calculator does not replace judgment; it arranges the data so patterns become easier to recognize.
How Sodium Levels Influences the Calculation
Serum sodium is key to the calculation because it supports the formula. Since sodium is the most abundant measured cation in the blood, any change in its concentration can alter the anion gap result. That does not mean sodium directly triggers the acid-base problem, but it can influence the final number and how the electrolyte balance is understood.
If sodium is low or high, the relationship between sodium, chloride, and bicarbonate shifts. The resulting lab result may still be meaningful, but the context matters. For example, a low sodium value can make the calculated gap less clear to interpret if the rest of the electrolytes are altered at the same time.
Albumin also is important here. Because albumin is a negatively charged protein, lower albumin can make the anion gap appear lower than it truly is. This is why albumin correction is sometimes used to estimate a corrected anion gap. In a patient with anion gap clinical significance hypoalbuminemia, the unadjusted number may miss the degree of underlying acid-base abnormality.
The corrected result is not a separate diagnosis. Rather, it is a correction factor applied to improve interpretation. This is especially important when the goal is to investigate a hidden cause of metabolic acidosis or to detect a subtle change in serum chemistry.
Typical, High, and Reduced Anion Gap Results
The expected range for the anion gap depends on the lab technique and whether potassium is included. That said, the result is usually categorized as anion gap within normal limits, increased anion gap, or reduced anion gap.
A anion gap within normal limits often suggests that the measured electrolytes are balanced in a typical way, though it does not automatically mean there is no problem. A high anion gap metabolic acidosis usually points to the presence of extra acids or unmeasured ions in the blood. A low anion gap is less common and may reflect low albumin, lab variation, or other issues that affect the measurement.
It is important to remember that “normal” is lab-specific. A result that seems borderline in one setting may be acceptable in another. This is why a full clinical interpretation should consider the specific blood test panel, the patient’s symptoms, and the broader pH balance.
In practical terms:
- Normal anion gap: may be seen when the electrolyte pattern does not suggest excess unmeasured acids. Increased anion gap metabolic acidosis: suggests extra acid accumulation or another process increasing the gap. Reduced anion gap: may indicate hypoalbuminemia, lab variation, or a less common abnormality.
Typical Causes of Altered Anion Gap Values
Various conditions may alter the anion gap and suggest a specific cause of metabolic acidosis. Among the most common are lactic acidosis, ketoacidosis, renal failure, and hypoalbuminemia.
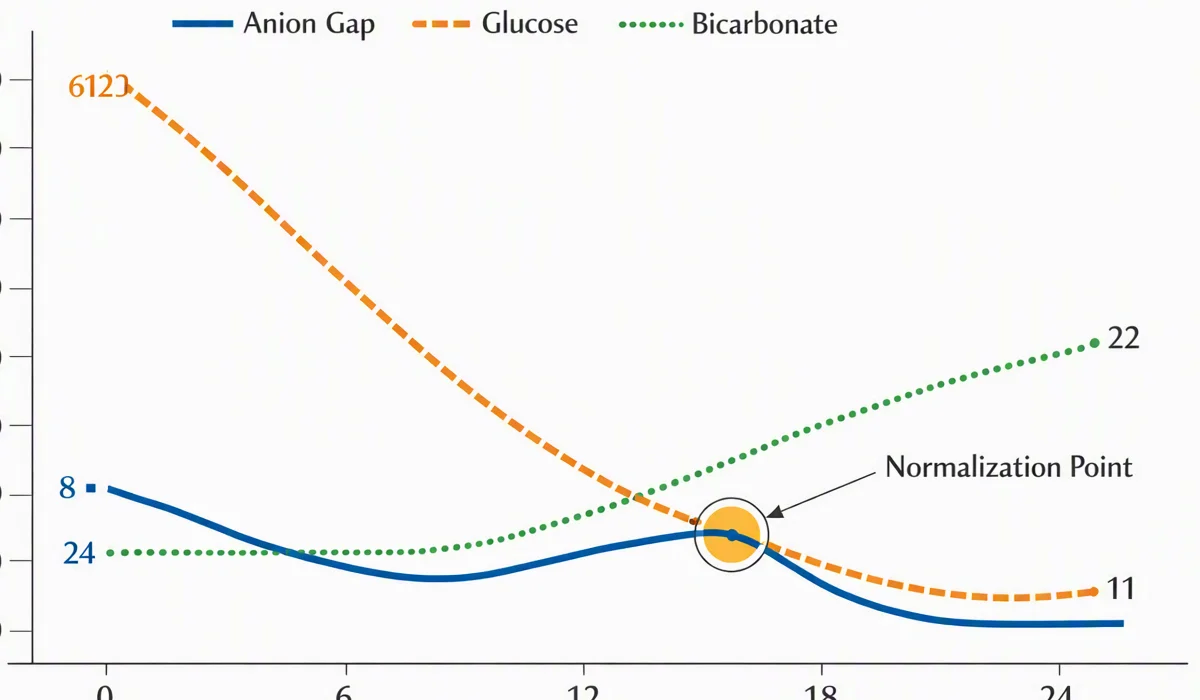
Lactic acidosis develops when lactate builds up faster than the body can clear it. This may happen with low oxygen delivery, severe illness, or other metabolic stress. Because lactate is an unmeasured anion, the gap may rise.
Ketoacidosis can develop when ketones accumulate, including in uncontrolled diabetes or prolonged fasting. These ketones add to the amount of unmeasured acids, often leading to high anion gap metabolic acidosis.
Renal failure can reduce the body’s ability to eliminate acids. As acid retention increases, the anion gap may become elevated. This result may be especially informative when paired with the rest of the electrolytes and kidney-related markers on the blood chemistry panel.
Hypoalbuminemia, on the other hand, anion gap in methanol poisoning may lower the measured gap. Because albumin contributes to the negative charge balance, low albumin can make the result appear deceptively normal or reduced. This is where albumin correction and the corrected anion gap become useful in clinical interpretation.
Additional causes may also occur, but these four are among the most commonly reviewed when reviewing an elevated or reduced anion gap.
Step-by-Step: Reading Calculator Output
Evaluating an anion gap calculator readout is more than submitting numbers and viewing a result. A careful process strengthens assessment and helps avoid errors.
Step 1: Review the electrolyte values. Check the serum sodium, chloride, and bicarbonate values from the electrolyte panel or blood chemistry panel. Ensure the units and sample are correct.
Step 2: Calculate the anion gap. Follow the anion gap formula to obtain the calculated value. Evaluate it with the lab’s reference range rather than using a universal cutoff.
Step 3: Consider albumin. If albumin is low, perform albumin correction to estimate the corrected anion gap. This may show a hidden elevation that would otherwise be missed.
Step 4: Match the pattern to the clinical picture. Identify signs of acid-base disorder, dehydration, kidney dysfunction, or other causes of metabolic disturbance. The result should fit the patient’s symptoms and other lab findings.
Step 5: Form a clinical interpretation. A single number is not enough. Integrate the anion gap with the rest of the serum chemistry, the history, and the physical findings to draw a reasonable conclusion.
A useful anion gap result is one that supports the full story, not one that is viewed in isolation.
Drawbacks of Anion Gap Calculation
Even though the anion gap is important, it has clear limits in diagnosis. The calculation depends on testing methods, lab handling, and the context in which the result is used.
One limitation is albumin correction. If albumin is not considered, the result may mislead the interpreter. This is especially relevant in patients with hypoalbuminemia, where the measured gap can be incorrectly low or normal.
Another limitation is lab variation. Different analyzers and reporting methods can produce slightly different reference intervals. A number that seems abnormal in one lab may fit inside a different lab’s expected range.
The calculation also does not directly identify the cause of the problem. It simply points to the possible presence of unmeasured ions or a shifted electrolyte pattern. Additional testing and context are needed to confirm the cause, whether that is lactic acidosis, ketone-related acidosis, renal failure, or something else.
Finally, the anion gap should not be used as a substitute for direct clinical care. It is best viewed as one part of a broader diagnostic approach to acid base balance and clinical assessment.
When to Seek Medical Review
Abnormal anion gap findings should be reviewed by a clinician, especially when they occur with concerning symptoms. Signs such as severe weakness, rapid breathing, confusion, vomiting, chest discomfort, or worsening illness may signal a serious metabolic acid buildup or another urgent condition.
An elevated or reduced result does not always mean emergency care is needed, but it does mean the test should be understood in context. If a blood chemistry panel shows a concerning pattern, prompt urgent evaluation may be appropriate to assess the underlying cause.
People with diabetes, kidney disease, infection, dehydration, or known electrolyte imbalances may need closer assessment if the anion gap is abnormal. The same applies if the result varies greatly from prior testing or doesn’t fit the patient’s clinical status.
In case of uncertainty, follow up with a clinician who can interpret the result alongside signs, exam findings, and other laboratory data.
FAQs About Anion Gap and Serum Sodium
What is an anion gap calculator with serum sodium used for?
An anion gap calculator with serum sodium is used to estimate the anion gap from common electrolytes on a blood chemistry panel. It assists with clinical assessment of acid-base problems, especially when evaluating metabolic acidosis or checking for a hidden metabolic abnormality.
How do you calculate the anion gap from sodium, chloride, and bicarbonate?
Use the anion gap formula: sodium - (chloride + bicarbonate). The serum sodium level, chloride concentration, and bicarbonate concentration are entered into the calculator to produce the final value.
Why does serum sodium matter in an anion gap calculation?
Serum sodium matters because it is the main measured cation in the formula. Changes in sodium can affect the final number and the way the acid-base balance is interpreted. Sodium also helps anchor the relationship between the measured electrolytes and the overall charge balance.
What does a high anion gap mean?
A high anion gap often suggests extra acids or unmeasured ions in the blood. Common causes include lactic acidosis, ketoacidosis, and renal insufficiency. It can be a clue to high anion gap metabolic acidosis, but the full clinical picture is needed for interpretation.
Can a regular anion gap still indicate a clinical issue?
Certainly. A normal anion gap does not rule out disease or an acid base problem. Some conditions may not change the gap much, and test result interpretation must take into account symptoms, other labs, and the patient’s general condition. Medical interpretation should always go beyond the number alone.