What the Anion Gap Measures
The anion gap is a practical way to evaluate acid-base balance by contrasting the main positive and negative components found in serum electrolytes. It assists clinicians spot hidden alterations in the body’s chemistry that may not be obvious from a basic electrolyte review alone.
At its core, the anion gap shows the difference between routinely measured cations and anions in a electrolyte panel. Because not every charged particle is directly measured, the result gives an indirect estimate of unmeasured anions. This makes it a useful marker in the diagnostic evaluation of an acid-base disorder, especially when metabolic acidosis is suspected.
An elevated or reduced gap does not diagnose a condition by itself. Instead, it serves as a indicator that can guide laboratory interpretation, prompt further testing, and support a broader review of serum chemistry and clinical findings. In practice, an anion gap calculator is a calculation tool that helps summarize these measured values quickly and accurately.
In what way the Anion Gap Calculator Functions
A anion gap calculator applies the main measured electrolytes from blood testing to determine the gap between cations and negatively charged ions. Common inputs are sodium, chloride, and bicarbonate. These values are usually reported as part of routine serum chemistry results.
anion gap clinical significanceThe usual form of the calculation matches sodium concentration with chloride concentration and bicarbonate level. Since sodium is the dominant measured cation and chloride and bicarbonate are key measured anions, the formula helps reveal shifts in electrolyte imbalance that may point to a metabolic problem.
This is particularly useful for clinical decision support because it offers a fast snapshot of anion gap interpretation. A clinician may use it to decide whether a patient’s symptoms and lab values fit a metabolic disturbance such as acidosis, whether the pattern suggests extra unmeasured anions, or whether the result is likely within the lab reference range.
Often, the calculator is used directly with the numbers from the lab report. That offers a straightforward way to interpret measured values without recalculating the same equation each time.
Measured Blood Electrolytes Needed for Accurate Calculation
To determine the anion gap accurately, you need the necessary serum electrolytes from the same blood draw if possible. The standard inputs are serum sodium, serum chloride, and serum bicarbonate. These values come from the electrolyte panel and are required for reliable laboratory interpretation.
Uniformity matters because the calculation assumes the numbers reflect the identical physiologic moment. If one result is outdated, drawn from a different sample, or affected by a testing issue, the gap may not accurately represent the patient’s current acid-base balance.
Besides the core values, clinicians often review related findings from the broader electrolyte panel. For example, an abnormal bicarbonate level may indicate buffering changes, while a shifted chloride concentration may help clarify whether the pattern looks like a normal anion gap issue or a high anion gap process.
Because the result depends on measured electrolytes, even small changes can change the final number. This is why careful review of the source lab values is an important step before drawing conclusions.
Step by Step Anion Gap Formula
The standard anion gap formula is easy to follow:
Na minus Cl minus HCO3
In this formula, Na stands for sodium, Cl represents chloride, and HCO3 represents bicarbonate. Some versions of the formula also include potassium, but the most common approach in routine practice is the one above. It is favored because it is simple, fast, and practical for everyday anion gap interpretation.
To apply the formula, start with the sodium concentration, then take away the chloride concentration, and deduct the bicarbonate level. The result is the anion gap. An Anion Gap Calculator performs this for you, reducing the chance of arithmetic mistakes and supporting efficient review of measured values.
The resulting number is then compared with the normal range or reference range provided by the laboratory. Different laboratories may use slightly different cutoffs depending on methodology and reporting standards, so it is best to interpret the result in the context of the specific lab reference range attached to the report.
For example, if sodium is 140, chloride is 102, and bicarbonate is 24, the formula produces an anion gap of 14. Whether that is considered normal depends on the lab’s established reference range and the overall clinical picture.
Standard, Increased, and Reduced Anion Gap Values
A finding within the usual reference range is often described as a within-range anion gap. This does not mean all is well by itself, but it suggests there is no obvious elevation in unmeasured anions based on the available results.
A elevated anion gap suggests an build-up of unmeasured acids or anions. This finding is commonly associated with metabolic acidosis and often prompts a deeper evaluation for underlying reasons. In this setting, the anion gap becomes a central part of anion gap interpretation and helps narrow the differential diagnosis.
A reduced anion gap is less common but can still be clinically relevant. It may reflect changes in protein levels, analytical errors, or shifts in measured electrolytes. Because low values can be missed, careful review is important before assuming the result is insignificant.
Interpreting these categories requires attention to the lab reference range. A value that seems abnormal in one context may be normal in another if the laboratory uses a different method or cutoff. That is why the reported reference range should consistently be checked before classifying the result.
Ultimately, the result is not interpreted in isolation. It should be paired with symptoms, the overall electrolyte panel, and the broader clinical question that triggered the test.
Common Causes of an Atypical Anion Gap
An unexpected result frequently points toward a specific metabolic imbalance. One of the main causes of a high anion gap is acid-base acidosis, where acids accumulate or buffering is reduced. Frequent examples include lactic acidosis, ketoacidosis, and renal failure.
Lactic acidosis can occur when tissues are underperfused, oxygen delivery is reduced, or metabolism is generally stressed. In these situations, lactic acid increases, and the anion gap may climb because of extra unmeasured acids.
Ketoacidosis is one more classic cause of high anion gap findings. When the body produces excess ketones, these acids raise the gap and may be seen with diabetes, starvation, or other states of reduced carbohydrate availability.
Renal failure can also elevate the gap because the kidneys are less able to clear acid loads effectively. As acids accumulate, the result may shift away from the normal anion gap and toward a high-gap pattern.
On the other end, a low anion gap may appear when albumin is reduced, when there is a testing artifact, or when unusual ions affect the calculation. Because the pattern is uncommon, it should be reviewed thoroughly with the rest of the serum electrolytes and the patient’s general condition.
Adjusting the Anion Gap for Albumin
Albumin is a key unmeasured anion in blood, so it has a strong effect on the calculated gap. When hypoalbuminemia is present, the measured result may seem lower than expected even if extra acids are present. That is why albumin correction is an important part of modern anion gap interpretation.
The corrected anion gap adjusts the result to account for low albumin. This matters because a patient with hypoalbuminemia may have a deceptively normal or only mildly elevated gap despite a significant acid-base problem. Without correction, the underlying disorder could be underestimated.
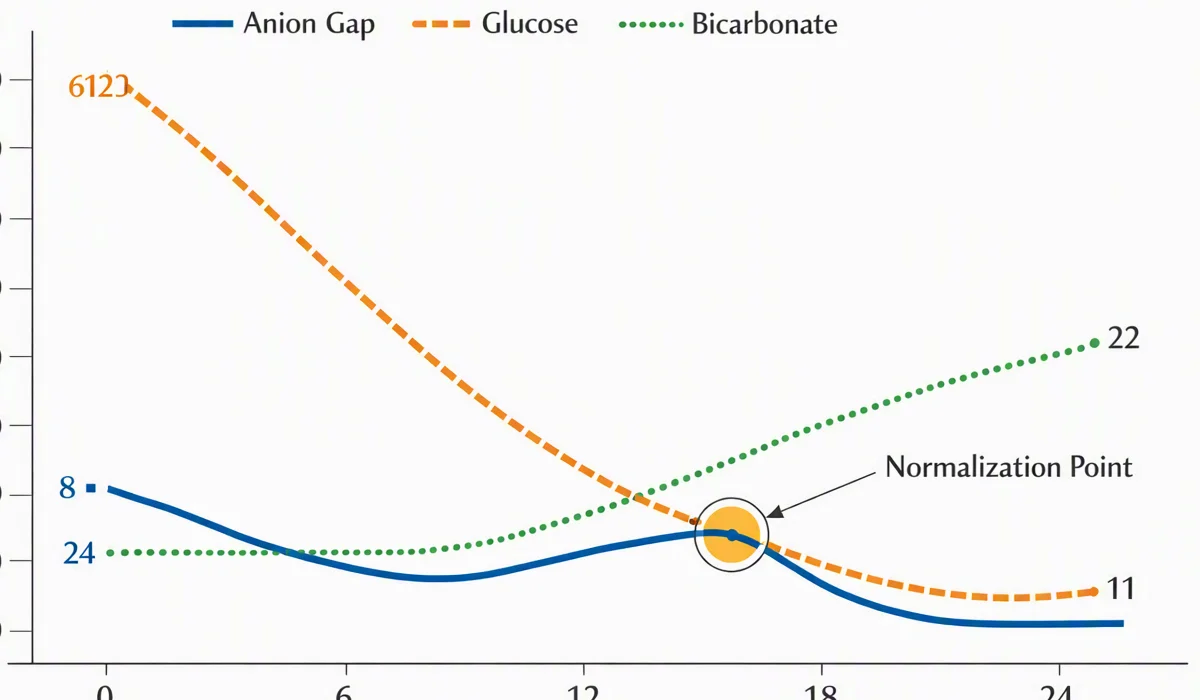
Using the corrected anion gap helps increase diagnostic accuracy, especially in patients with chronic illness, poor nutrition, inflammation, or other conditions associated with low protein levels. In these cases, the calculator should be used as part of a broader review rather than as a stand-alone number.
Albumin correction is not always required, but it is often beneficial when the measured result and the clinical picture do not match. When the gap seems unexpectedly low or borderline, checking the albumin level can enhance interpretation and reveal hidden metabolic changes.
How to Read Results in Patient Care Context
The ideal way to interpret an anion gap calculator is together with the full clinical picture. A one value can suggest a direction, but an definitive diagnosis depends on symptoms, medical history, and other labs. In practice, interpretation often includes the arterial blood gas, the electrolyte panel, and other indicators of organ function.
The arterial blood gas can show whether the patient has acidemia or alkalemia and whether respiratory compensation is underway. When combined with the electrolyte panel, it helps identify the specific acid-base disorder. This is especially important if the bicarbonate is low or if the patient has signs of shock, dehydration, toxin exposure, or kidney dysfunction.
A high anion gap with low bicarbonate often supports the presence of metabolic acidosis. But not all metabolic acidosis is the same. Some cases are related to lactic acid, some to ketones, and others to impaired renal clearance. The pattern of serum electrolytes can help identify which mechanism is most plausible.
A normal value does not always exclude disease. Take a look at the site here For example, mixed disorders can mask abnormalities, and a low albumin level can blunt the expected rise. That is why anion gap interpretation should be paired with clinical examination, diagnosis-focused testing, and careful review of all available measured values.
Limitations and Frequent Calculation Errors
Even though the anion gap is easy to calculate, several issues can affect calculation accuracy. One of the most common is measurement error. If the source lab result is wrong, contaminated, or collected improperly, the final number may not reflect the patient’s true status.
Lab variation is another important factor. Different instruments and reporting methods can produce slightly different values for sodium, chloride, or bicarbonate. As a result, the same patient may have a different result depending on the laboratory, making the lab reference range essential for interpretation.
Another typical problem is relying on mismatched results. If sodium was drawn at one time and chloride or bicarbonate at another, the value may be misleading. The preferred method is to use a single, consistent electrolyte panel whenever practical.
Readers should also avoid overinterpreting a borderline abnormal result without clinical context. A small shift may be due to routine variation rather than a true metabolic disturbance. Likewise, a clearly abnormal value should prompt review of the entire clinical situation rather than a reflex conclusion based on the calculator alone.
In short, the tool is only as good as the input. Careful review of serum electrolytes, attention to measurement error, and awareness of lab variation are key to dependable anion gap interpretation.
Frequently Asked Questions
What is a normal anion gap?
The anion gap normal range depends on the laboratory method and the reported reference range. In many settings, the value is considered normal when it falls within the lab’s stated cutoff. Because methods vary, the most accurate interpretation is the one that matches the specific lab reference range listed with the result.
How do you calculate the anion gap from measured electrolytes?
Use the standard anion gap formula: Na minus Cl minus HCO3. Enter the measured sodium, chloride, and bicarbonate values from the same electrolyte panel. An anion gap calculator makes this process faster and reduces the chance of arithmetic mistakes.
Why is albumin used to correct the anion gap?
Albumin is a major unmeasured anion, so low levels can make the gap appear falsely low. Albumin correction helps produce a more accurate corrected anion gap, especially in patients with hypoalbuminemia. This improves the detection of hidden acid-base abnormalities.
What causes a raised anion gap?
Typical high anion gap causes include lactate acidosis, ketosis-related acidosis, and renal insufficiency. Such conditions elevate hidden acids or impair acid clearance, leading to metabolic acidosis and a elevated calculated gap.
Is a low anion gap clinically significant?
Absolutely. A decreased anion gap can be significant in practice, especially when linked to hypoalbuminemia, a testing issue, or other abnormalities in serum electrolytes. It should not be ignored, particularly if the result does not fit the rest of the acid-base equilibrium picture.