What Does Mean the Anion Gap?
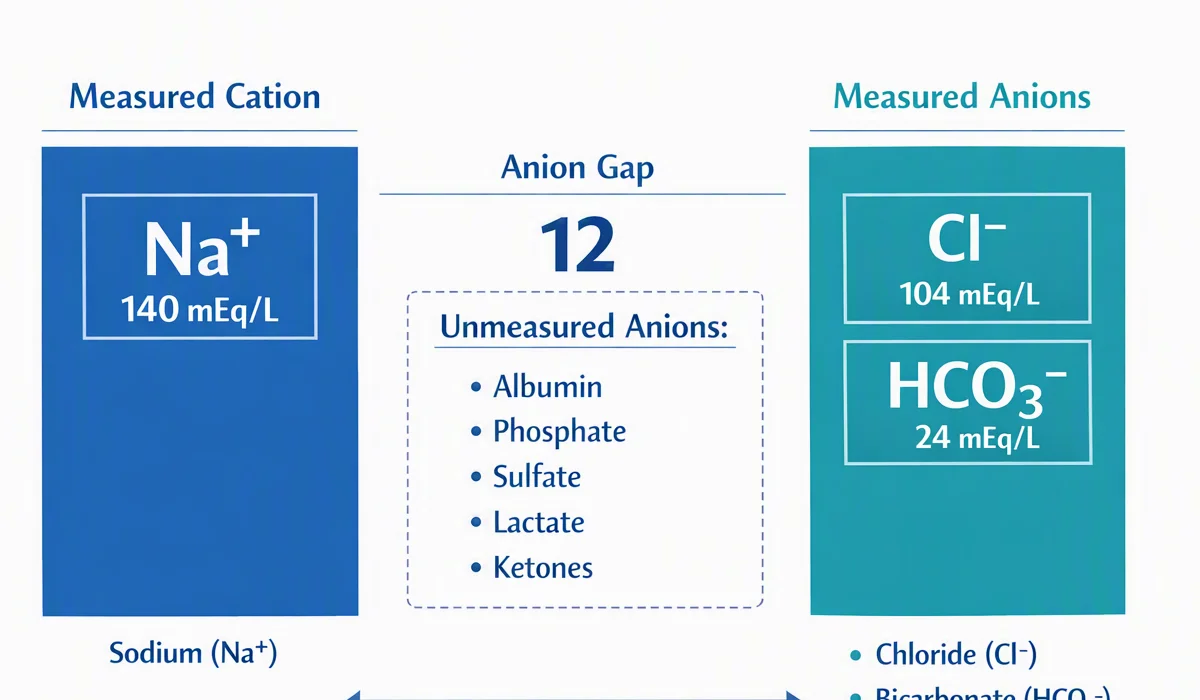
This anion gap is a computed value that helps healthcare providers evaluate acid-base balance by comparing the major measured cations and anions in the blood. It is commonly obtained from routine serum electrolytes, especially sodium, chloride, and bicarbonate. Because the body must maintain electrical neutrality, the anion gap estimates the difference between measured positively charged and negatively charged particles, indirectly reflecting unmeasured ions.
In clinical practice, the anion gap is especially useful when evaluating metabolic acidosis. A shift in the gap often points toward excess acids, lost bicarbonate, or laboratory patterns that require a broader diagnostic approach. As it uses routine lab data, it is one of the simplest tools for identifying an acid-base disorder and limiting the differential diagnosis.
While the exact number can vary based on the lab’s reference range, a normal result usually implies that measured cations and anions are in expected balance. A higher-than-expected result can indicate high anion gap acidosis, while a normal value in the setting of acidosis may indicate normal anion gap or hyperchloremic processes. That distinction is central to clinical interpretation.
How the Anion Gap Calculator Works
An anion gap calculator simplifies the anion gap formula so that clinicians can rapidly interpret laboratory values and assess for an electrolyte imbalance. The standard formula is:
Anion gap = sodium − (chloride + bicarbonate)
Some versions include potassium, but most bedside interpretation relies on the streamlined formula above. The calculator uses serum sodium, serum chloride, and serum bicarbonate to determine the amount of unmeasured anions in the plasma. A wider gap usually suggests presence of organic acids or other unmeasured substances.
The calculator becomes even more helpful when albumin is abnormal. Because albumin is a negatively charged protein and a major unmeasured Discover more here anion, low albumin can make the gap appear falsely normal. That is why many clinicians apply albumin correction before final interpretation. The output is often a corrected anion gap, which gives a more accurate picture of the patient’s underlying acid-base status.
In real-world use, the calculator supports rapid blood gas analysis and complements the exam of acid-base patterns. It does not replace clinical judgment, but it helps with the first step in recognizing metabolic acidosis, especially when the cause is not immediately obvious.
Why the Anion Gap Matters in Acid-Base Balance
The anion gap matters because it assists in distinguishing different kinds of acid-base balance issues. When metabolic acidosis is present, the gap can point toward either a high anion gap or a normal anion gap profile. This difference is important because the causes, urgency, and treatment strategies are often different.
In high gap acidosis, the body has built up unmeasured acids. In normal gap acidosis, bicarbonate is often lost and replaced by chloride, which maintains the gap but still results in acidemia. This is why the anion gap is not just a number; it is a framework for understanding the underlying buffering system and how the body reacts to an acid-base disorder.
It also can reveal a mixed disorder. For example, a patient may have a metabolic acidosis and a second process affecting pH, such as respiratory compensation that is insufficient or exaggerated. In these cases, the anion gap adds structure to the clinical interpretation of the patient’s labs and symptoms.
Because the gap is tied to measured and unmeasured ions, it is a helpful connection between routine chemistry testing and deeper physiologic reasoning. That makes it a essential tool in both routine medicine and urgent evaluation.
How to Read a Elevated Anion Gap
A increased anion gap usually means that hidden acids are present in excess. This is a common finding in many severe causes of metabolic acidosis, and it should trigger a careful search for the origin of the acid anion gap clinical significance load.
Frequent causes include lactic acidosis, ketoacidosis, renal failure, and toxic ingestions. In lactic acidosis, tissue reduced blood flow, sepsis, seizures, or major physiologic stress can raise lactate production. In ketoacidosis, ketone bodies build up when insulin is insufficient or when starvation and alcohol-related states disrupt metabolism. Renal failure can reduce acid excretion, allowing unmeasured acids to collect. Toxic alcohol ingestion is another notable cause because substances such as methanol or ethylene glycol generate acid metabolites that raise the gap.
When the gap is elevated, the next question is not just “Is it high?” but “Why is it high?” That requires combining the anion gap with the patient’s history, exam, and other lab data. A patient with acidemia, elevated lactate, and hypotension may have lactic acidosis. Someone with hyperglycemia or starvation may point toward ketoacidosis. Kidney function tests, osmolar calculations, and toxicology clues may be needed in other scenarios.
A high gap is especially concerning because it can signal a critical condition that needs prompt treatment. The anion gap calculator helps detect the pattern early, but the clinician must then relate it to the patient’s overall presentation.
How to Interpret a Typical Anion Gap
A normal gap doesn't eliminate metabolic acidosis. Instead, it typically indicates loss of bicarbonate with a compensatory rise in chloride, leading to hyperchloremic acidosis. This is often called normal-anion-gap acidosis.
One of the most common causes is gastrointestinal fluid loss, where the body loses bicarbonate-rich intestinal fluid. Another key cause is renal tubular acidosis, in which the kidneys cannot manage acid or bicarbonate normally. In both situations, the loss of bicarbonate is central, but the anion gap remains in the expected range because chloride rises to preserve electroneutrality.
This picture can be easy to overlook if attention is placed only on the pH. A patient may be acidemic with low bicarbonate but still have a normal gap. For that reason, a full review of blood electrolytes matters. The serum chloride level often goes up relative to bicarbonate, creating the lab pattern that supports a normal-gap process.
Normal-gap patterns are also useful when evaluating treatment effects. For example, after a high-gap acidosis begins to resolve, the gap may normalize while bicarbonate remains low, or the patient may develop a mixed picture. Thoughtful follow-up prevents misclassification and supports better medical interpretation.
Albumin level Adjustment and Additional Important Corrections
Albumin is among the most important elements to consider when interpreting the anion gap. Because albumin contributes substantially to the pool of unmeasured anions, hypoalbuminemia can decrease the measured gap and mask a clinically significant acidosis. In these cases, albumin correction is necessary.
The resulting corrected anion gap gives a better picture of the true acid burden. Without this adjustment, a patient may look to have a normal gap even when a high-gap process is present. This is especially important in ill patients with inflammation, malnutrition, liver disease, or critical illness, where low serum albumin is often seen.
Albumin’s role is tied to protein binding and the overall charge balance in plasma. When albumin falls, the baseline anion gap falls too. That means the lab result has to be interpreted in context rather than as an isolated number. A clinician using an anion gap calculator should therefore check whether the tool includes an albumin adjustment or whether correction must be done separately.
Other adjustments may also matter depending on the setting, but albumin is the major one in routine practice. It is a reminder that not all “normal” results are truly normal. If the patient has hypoalbuminemia, a corrected value may reveal hidden high gap acidosis that changes the differential diagnosis and treatment priorities.
Stepwise: How to Evaluate Acid-Base Balance
A practical approach begins with the complete data set: serum electrolytes, an arterial blood gas, and the clinical context. The goal is to determine whether there is acidemia or alkalemia, whether the problem is metabolic or respiratory, and whether the anion gap helps explain the pattern.
Initially, review the pH on the blood gas. If the pH is low, acidemia is present. Next, examine bicarbonate and carbon dioxide to decide whether the primary problem is metabolic or respiratory. If bicarbonate is low, metabolic acidosis is likely. At that point, calculate or review the anion gap using sodium, chloride, and bicarbonate.
In the second step, assess whether respiratory compensation is appropriate. The lungs often reduce carbon dioxide in response to metabolic acidosis. If compensation is not as expected, another process may be present. This is where blood gas analysis and the electrolyte panel should be interpreted together rather than separately.
Then, decide whether the pattern is high-gap or normal-gap. A high-gap pattern should trigger evaluation for lactic acidosis, ketoacidosis, renal failure, or toxic alcohol exposure. A normal-gap pattern should raise suspicion for diarrhea, renal tubular acidosis, or other sources of bicarbonate loss.
Lastly, review whether albumin is low and whether a corrected anion gap is needed. This step improves accuracy and can reveal a mixed disorder that would otherwise be overlooked. In short, the process is: assess pH, identify the primary disorder, calculate the gap, correct for albumin, and then interpret the result in context.
Common Errors in Anion Gap Interpretation
One of the most common of the main errors is overlooking lab error or specimen issues. One abnormal reading should always be be checked against the other values of the panel and the clinical context. If the numbers do not make physiologic sense, repeat testing may be necessary before drawing conclusions.
Another frequent error is overlooking the reference range used by the laboratory. Various analyzers and institutions may have slightly different normal ranges, so the same numeric result can be interpreted differently depending on the setting. For this reason the anion gap should never be treated as a standalone diagnosis.
Another issue is that it is easy to miss a mixed acid-base disorder. For instance, a patient may have a high anion gap and a concurrent metabolic alkalosis, or a normal gap with a respiratory process superimposed. The delta gap is valuable here because it compares the change in the anion gap to the change in bicarbonate and can suggest whether additional processes are present.
Another pitfall is forgetting that low albumin changes the baseline. If hypoalbuminemia is present, the measured anion gap may downplay the severity of the disturbance. Proper albumin correction minimizes this risk and improves diagnostic reliability.
Situations for Using an Anion Gap Calculator
An anion gap calculator is particularly useful when a quick, accurate assessment is needed for clinical decision making. It is especially valuable during emergency evaluation when a patient presents with vomiting, altered mental status, shock, dyspnea, or signs of acidemia. In these situations, rapid recognition of an acid-base disorder can guide immediate care.
The calculator is also important in critical care, where serial labs are reviewed often and subtle changes can matter. Patients with sepsis, kidney dysfunction, diabetes, intoxication, or gastrointestinal losses often have variable electrolyte patterns. A calculator helps arrange those values into a usable interpretation.
In everyday clinical use, the tool facilitates a more structured approach to any suspected acid-base disorder. It can help differentiate metabolic acidosis from other problems, recognize when albumin correction is needed, and guide next-step testing. Because it links electrolytes, albumin, and the broader clinical picture, it is not just a math aid; it is part of the diagnostic workflow.
For best results, use it alongside the patient’s symptoms, medications, kidney function, glucose, lactate, ketones, and blood gas results. That broader context turns a number into actionable information.
Frequently Asked Questions About Anion Gap and Acid-Base Balance
What is the anion gap and why is it important?
The anion gap is a computed value from sodium, chloride, and bicarbonate that helps evaluate acid-base balance. It is important because it helps identify metabolic acidosis and differentiate between high anion gap and normal anion gap patterns, which have varying causes and treatment priorities.
How do you calculate the anion gap from lab values?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate: sodium − (chloride + bicarbonate). An Anion Gap Calculator performs this calculation for you using serum electrolytes. If albumin is low, albumin correction may be needed for a more accurate result.
What does a high anion gap mean in acid-base balance?
A high anion gap usually means there are additional unmeasured acids in the blood. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohol ingestion. It often signals a medically significant form of metabolic acidosis that needs prompt evaluation.
How does low albumin affect the anion gap?
Hypoalbuminemia decreases the calculated anion gap because albumin is a key unmeasured anion. That can make a true high-gap process look normal. Using a corrected anion gap helps compensate for this effect and enhances clinical interpretation.
Can a normal anion gap still occur with metabolic acidosis?
Absolutely. A normal anion gap can still be seen with metabolic acidosis, especially when there is bicarbonate loss replaced by chloride. Common causes include diarrhea and renal tubular acidosis, often described as hyperchloremic acidosis or normal gap acidosis.