What Is Delta Gap?
The delta gap is a useful way to evaluate whether an acid-base condition is restricted to one process or contains more than one pattern at the same time. It is most often used when a patient has acidosis and the anion gap is elevated. In that setting, the delta gap helps estimate whether the drop in bicarbonate matches the rise in the anion gap.
That comparison matters because a one-time episode of metabolic acidosis does not always describe the full clinical significance of the lab results. If the anion gap rises more than expected, or if bicarbonate falls more than expected, the result may suggest a combined acid-base disorder. In other words, delta gap is a fast check for hidden complexity in acid-base balance.
The concept is closely related to the anion gap delta and the delta ratio. These measurements compare the shift in the anion gap to the change in bicarbonate. They are not used to replace the rest of the evaluation, but they add a useful layer of analysis when interpreting electrolytes.
In plain terms:
- The anion gap shows whether unmeasured acids may be present. The delta gap shows whether the bicarbonate change fits that rise. The result helps identify a possible hidden second disorder.
How an Anion Gap Calculator Works
An anion gap calculator is a utility that employs basic electrolyte measurements to determine the anion gap efficiently. The calculation is based on the values for serum sodium, serum chloride, and serum bicarbonate. Most calculators apply the standard formula:
Anion gap = Serum sodium - (Serum chloride + Serum bicarbonate)
This measurement assists in identifying whether there is an elevated level of unmeasured anions in the blood. When the result is greater than the expected reference range, it may indicate the presence of metabolic acidosis, especially high anion gap metabolic acidosis.
Here is why each value matters:
- Serum sodium provides the main positive charge in the calculation. Serum chloride accounts for one major negative charge that shifts in response to acid-base shifts. Serum bicarbonate reflects buffering capacity and often drops in metabolic acidosis.
A calculator can give a quick result, but the clinical value comes from interpretation. The same anion gap number can have distinct implications depending on the patient’s electrolytes, symptoms, and arterial blood gas findings.
For example, if serum bicarbonate is low and chloride is high, the pattern may match normal anion gap metabolic acidosis. If bicarbonate is low and the anion gap is elevated, the evaluation turns toward high-gap causes and possible mixed patterns.
Delta Gap Formula & Step-by-Step Calculation
The delta gap equation matches the observed rise in the anion gap with the predicted fall in bicarbonate. The goal is to estimate whether the change is balanced or whether a different issue is affecting the result.
The delta gap = Elevation in anion gap - Decrease in bicarbonate
Another way to express the process is through the ratio calculation:
Delta ratio = (Measured anion gap - reference anion gap) ÷ (reference bicarbonate - Measured bicarbonate)
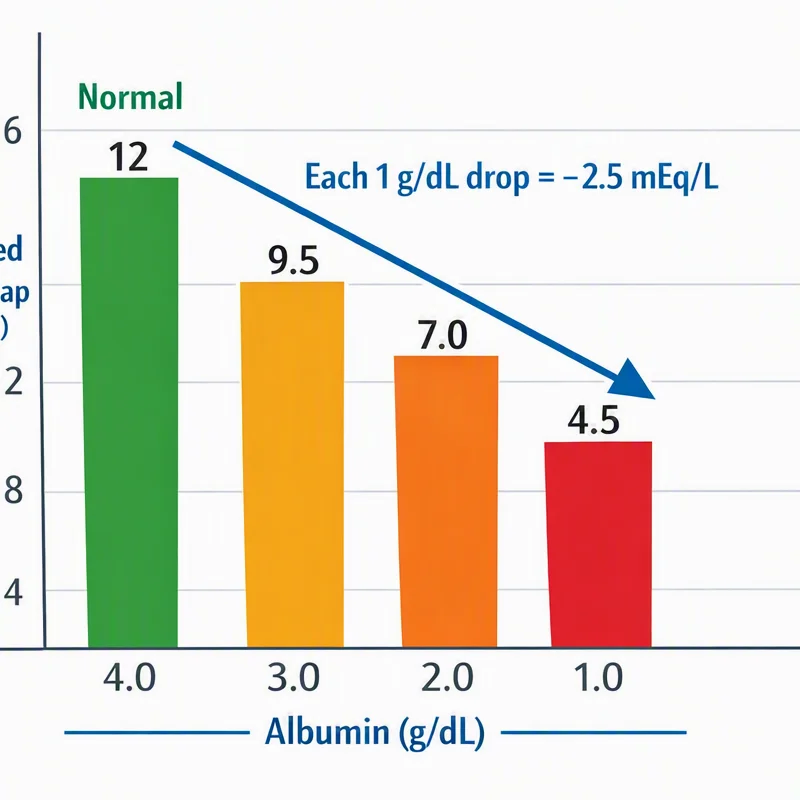
Before you calculate, you need a reference range for the “normal” values used in in the comparison. Many providers use a normal anion gap of about 12 mEq/L and a normal bicarbonate of about 24 mEq/L, but local lab ranges may differ. For that reason the reference range should always be checked against the actual laboratory report.
In steps:
Find the measured anion gap from the anion gap calculator. Subtract the normal anion gap to get the anion gap difference. Calculate the bicarbonate deficit by subtracting the measured bicarbonate from the normal bicarbonate. Compare the two values using the delta gap formula or delta ratio.Worked example:
Suppose a patient has:
- Serum sodium: 140 Serum chloride: 100 Serum bicarbonate: 14
Initially, calculate the anion gap:
140 - (100 + 14) = 26
If the normal anion gap is 12, then the delta anion gap is:
26 - 12 = 14
If the normal bicarbonate is 24, then the bicarbonate deficit is:
24 - 14 = 10
The delta ratio is then:
14 ÷ 10 = 1.4
A value in this range often suggests a typical high anion gap pattern, but the full diagnosis still depends on the patient’s overall picture. The value becomes more useful when compared with the expected pattern for the suspected cause.
How to Interpret Delta Gap Results
Delta gap assessment is most useful after confirming high anion gap metabolic acidosis. The result helps determine whether the acid-base disorder is isolated or whether a coexisting process is present.
General interpretation uses the idea that the increase in anion gap should roughly match the decrease in bicarbonate. If the match is unexpected, the result may suggest an additional disorder.
Common interpretation patterns:
- Normal or near-normal delta ratio: often suggestive of uncomplicated high anion gap metabolic acidosis. Low delta ratio: may suggest an added normal anion gap metabolic acidosis, because bicarbonate is falling more than the gap is rising. High delta ratio: may suggest a concurrent metabolic alkalosis or chronic compensation, because the bicarbonate is not as reduced as expected for the size of the gap.
This is where mixed acid-base disorder detection becomes important. A single lab result can hide two different processes moving in opposite directions. The delta approach helps expose that pattern.
For example, a patient with elevated anion gap and severe diarrhea could have both high-gap acidosis and normal-gap acidosis. Another patient with vomiting and ketoacidosis could have high-gap acidosis plus metabolic alkalosis. In both cases, the delta result offers a clue that the acid-base disorder is not simple.
Always interpret the result with the arterial blood gas, symptoms, and the rest of the chemistry panel. Delta calculations are a tool for evaluation, not a final diagnosis.
Typical Causes of Abnormal Delta Gap
An abnormal delta gap frequently suggests a source of high anion gap metabolic acidosis or a mix of problems. The important step is to relate the finding with likely causes and the patient’s medical context.
Lactic acidosis is a frequent cause. In this scenario, lactate accumulates and raises the anion gap. If the bicarbonate drop is greater than predicted, a second process may also be involved.
Ketoacidosis is another classic reason. This can occur with diabetic ketoacidosis, starvation, or alcohol-related situations. The anion gap becomes increased as ketones rise, and the delta gap can help identify whether there is also a normal-gap acidosis or a metabolic alkalosis.
Renal failure can also cause a high gap because the kidneys are not as able to clear acids. In advanced renal dysfunction, the pattern may be complicated by changes in chloride and bicarbonate management.
Toxic ingestion is an key consideration when the anion gap is elevated. Certain toxins can create severe metabolic acidosis with an abnormal delta result. In these instances, the delta gap should be read alongside history, exam findings, and the broader metabolic picture.
Additional causes of abnormal results can include:
- Severe dehydration with electrolyte shifts Multiple simultaneous disorders affecting chloride and bicarbonate Compensation patterns that change the apparent bicarbonate deficit
The real-world question is not only “Is the anion gap elevated?” but also “Does the bicarbonate change fit the gap change?” That assessment is where the delta gap becomes useful.
Delta-gap versus Anion Gap: What Makes Them Different?
The anion gap and delta ratio are closely linked, but they answer different issues. The anion gap asks whether unmeasured anions are present in excess. The delta gap asks whether the extent of the bicarbonate change aligns with the size of the anion gap change.
Think of it this way:
- The anion gap is the primary screen for an acid-base problem. The delta ratio and delta gap are second-step tools for deeper acid-base evaluation.
The delta ratio is often used interchangeably with delta gap in clinical discussions, although the exact formula may be written differently. Both methods aim to compare the elevation in anion gap with the decrease in bicarbonate. That comparison helps reveal whether a second disorder is present.
For acid-base evaluation, the difference matters because the anion gap alone may fail to detect a hidden pattern. A normal-looking bicarbonate level can conceal a mixed disorder, and a high gap can appear with another process that shifts chloride or bicarbonate in the opposite direction.
So, the main difference is purpose:
- Anion gap: identifies an abnormal measurement pattern. Delta gap: analyzes the pattern and tests for mixed disorders.
When to Apply Delta Gap in Medical Practice
Delta gap is particularly useful when the clinical concern is focused on metabolic acidosis and the lab values are already indicating a high-gap process. It is not often the first calculation, but it is a valuable follow-up tool when the pattern is not obvious.
You should use delta gap when:
- The patient has abnormal electrolytes and low serum bicarbonate. The arterial blood gas suggests acidemia and the chemistry panel points to metabolic acidosis. You need to determine whether there is a hidden second disorder. The patient may have metabolic alkalosis alongside acidosis.
In practice, this is a clinical assessment tool that works best after the initial diagnosis of metabolic acidosis is already established. It helps answer the question: “Is this only a high-gap process, or is something else happening too?”
Delta gap is particularly valuable when:
- There is likely lactic acidosis or ketoacidosis. The bicarbonate level seems too low for the gap. The chloride level appears to be changing the acid-base pattern. The patient’s symptoms do not fit a simple one-disorder explanation.
Because this calculation depends on precise lab values, small measurement differences can alter the result. Always verify the serum sodium, serum chloride, and serum bicarbonate values before making a decision.
FAQs About Delta Gap
How do you work out delta gap from an anion gap calculator result?
To begin, run the anion gap calculator to determine the anion gap from serum sodium, serum chloride, and serum bicarbonate. Next subtract the normal anion gap to get the delta anion gap. Afterward, subtract the measured bicarbonate from the normal bicarbonate to get the bicarbonate deficit. Contrast the two values using the delta gap formula or the delta ratio. This gives you a quick estimate of whether the acid-base pattern is compatible or mixed.
What does an elevated delta gap indicate?
A high delta gap often means the rise in anion gap is larger than the fall in bicarbonate. That can suggest an additional process such as metabolic alkalosis or chronic compensation. It may also mean the expected relationship between the gap and bicarbonate is not fitting the usual pattern for metabolic acidosis. The result should be interpreted with the rest of the clinical data, not alone.
How does delta gap differ between delta gap and delta ratio?
Both terms are used to compare the change in anion gap with the change in bicarbonate. The delta ratio is usually written as a ratio, while delta gap may refer to the same comparison in a slightly different format. In practical acid-base evaluation, both aim to detect a mixed acid-base disorder and clarify the pattern behind high anion gap metabolic acidosis.
Can a normal anion gap still have a mixed acid-base disorder?
Yes. A normal anion gap does not rule out a mixed disorder. A patient can have normal anion gap metabolic acidosis plus another condition, https://anion-gap-reader771.wpsuo.com/how-to-calculate-anion-gap or one process can offset another and create a misleading result. That is why the overall acid-base balance, arterial blood gas, and electrolyte pattern all matter during evaluation.
At what point should delta gap be applied in metabolic acidosis?
Delta gap should be used after metabolic acidosis has been identified and the anion gap is elevated or potentially changing the pattern. It is especially helpful when you want to determine whether the result reflects only high anion gap metabolic acidosis or whether there is also normal anion gap metabolic acidosis or metabolic alkalosis. In short, use it when the diagnosis needs a deeper comparison of bicarbonate and the anion gap.