What’s the Anion Gap?
The anion gap anion gap clinical significance is a simple but useful value derived from routine electrolytes on a serum chemistry panel. It assists clinicians in identifying hidden acids or other unmeasured anions that may be affecting a patient’s chemistry. In practical terms, the anion gap value supports clinical interpretation of blood chemistry by showing whether there may be an underlying electrolyte imbalance or metabolic acid-base disorder.
The classic anion gap formula compensates positively charged ions with negatively charged ions, most commonly using serum sodium, serum chloride, and serum bicarbonate. In many lab systems, potassium may also be included, although the most common version excludes it. The result is not a direct measurement of acid, but a diagnostic aid that can suggest conditions that require more detailed acid-base evaluation.
Because the anion gap is calculated from standard laboratory results, it is widely used in bedside and outpatient patient assessment. A considered interpretation of the number can suggest whether there is a high anion gap pattern, a normal anion gap state, or an unexpectedly low anion gap that deserves confirmation.
Why the Adjusted Anion Gap Counts
This standard anion gap is valuable, but it can be deceptive when albumin is decreased. Since serum albumin contains a substantial amount of negative charge in the blood, hypoalbuminemia can lower the measured gap even when important acids are present. For this reason the corrected anion gap is important: it calibrates the number so the clinician can more accurately evaluate acid-base balance.
If you skip albumin adjustment, a patient with significant metabolic acidosis may look to have a normal result. That is especially important in hospitalized or critically ill patients, where albumin may decline because of inflammation, poor nutrition, fluid shifts, or illness severity. In these cases, the corrected value enhances diagnostic interpretation and enables more accurate decisions.
The corrected result is not meant to override clinical judgment. Instead, it supplies context to the raw calculation and improves clinical significance. For example, a “normal” anion gap in a patient with low albumin may still conceal a true acid load. That is why correction is often a truer reflection of real physiology than the unadjusted number alone.
How the Anion Gap Calculator Operates
The Anion Gap Calculator streamlines the anion gap calculation so healthcare providers and learners can quickly calculate the gap from routine blood chemistry. Most calculators apply a simple calculation formula based on serum sodium, serum chloride, and serum bicarbonate. In its usual form, the calculation is:
anion gap = sodium - (chloride + bicarbonate)Some versions also include potassium, which slightly changes the result. A potassium-inclusive formula may be written as:
anion gap = sodium + potassium - (chloride + bicarbonate)Both versions are applied in practice, but the sodium-based formula is the most common. The calculator does not identify disease by itself; it is a diagnostic aid that helps interpret the broader pattern of blood chemistry. When paired with the patient’s presenting features, pH, lactate, ketones, kidney function, and medication history, it becomes part of a comprehensive clinical interpretation.
Because the anion gap represents the difference between measured cations and measured anions, it indirectly suggests the presence of unmeasured anions. That is why it is so helpful in detecting metabolic problems that might otherwise be missed on a standard serum chemistry panel.
Calculating the Anion Gap for Albumin
The revised gap takes into account the influence of blood albumin. Since albumin is a major negatively charged protein, reduced levels can make the gap appear falsely low or normal. The albumin correction raises the number upward when albumin is below the normal reference interval.
A common correction approach adds a fixed amount for each gram per deciliter that albumin is below the expected level. Some institutions may use slightly different formulas, so the exact adjustment may vary. In general, the lower the albumin, the greater the need for adjustment. This is the practical heart of gap correction.
Why does this matter so much? Because low albumin can mask a true acidotic state. A patient may have a standard anion gap that looks normal, yet the corrected value reveals a clinically meaningful elevation. That difference can change the workup, the urgency https://anion-gap-lookup809.timeforchangecounselling.com/interpreting-anion-gap-in-ckd of treatment, and the interpretation of the overall acid-base state.
Reviewing the corrected result is especially important when comparing values against a lab’s reference interval. A “normal” uncorrected number may no longer be normal after albumin correction. For this reason, the corrected calculation is often a more reliable reflection of the patient’s true clinical significance than the raw value alone.
Typical Causes of an Elevated Anion Gap
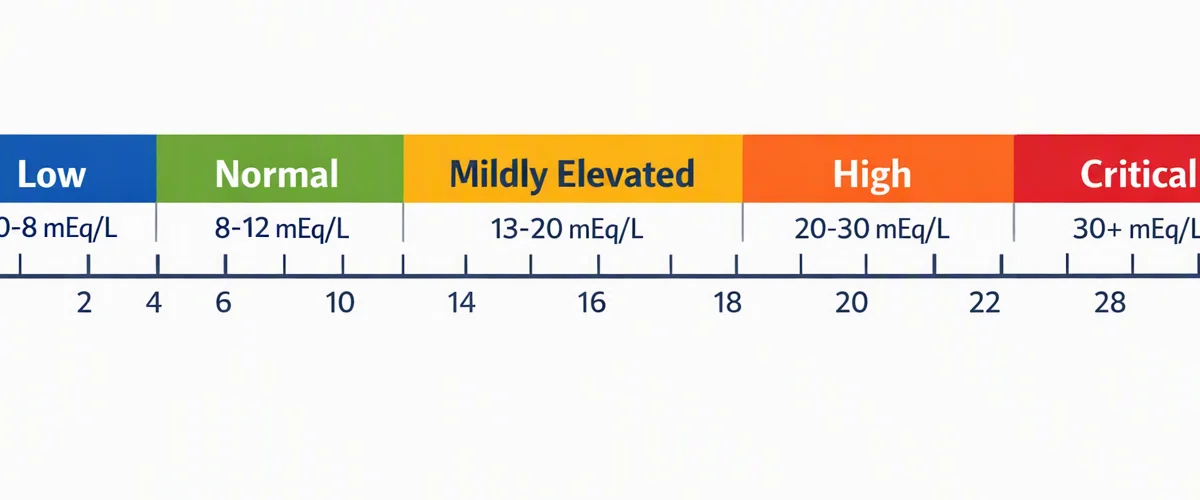
An raised gap commonly points to presence of acid compounds or uncounted anions. The leading contributors include lactic acidosis, ketone acidosis, kidney failure, and some toxic ingestions. These conditions can each disturb the acid-base balance and produce a typical elevated anion gap pattern.
Lactic acidosis can develop when tissues are not adequately perfused or under metabolic stress, leading to higher lactate production. Ketotic acidosis occurs when ketone bodies accumulate, often in diabetes, alcohol-related illness, or prolonged fasting. Renal insufficiency can raise the gap because the kidneys are unable to eliminate acids effectively.
Poisonous alcohols are another significant cause of increased values. Ingestions involving methanol, ethylene glycol, and related compounds can produce severe acid-base derangements that may be life-threatening. Aspirin-related compounds can also alter the pattern, sometimes creating a mixed disorder that requires careful review of the full clinical picture.
Because these disorders can overlap, the anion gap should be viewed as an element of the puzzle. It supports clinical assessment, but it does not replace history, exam, medication review, and targeted testing. The calculator is most useful when it helps determine the next step in the diagnostic process.
How to Understand Low or Normal Anion Gap Results
A decreased anion gap is rarer than an high value, but it can still be important. Before assuming disease, the first question is whether the result is genuine. Laboratory error is one of the most usual explanations, so rerunning the test is often the first step if the result is unexpected.
A within-range anion gap does not always mean there is no acid-base disorder. If the patient has hypoalbuminemia, the true gap may be missed until an albumin correction is applied. That is why the modified number can be more revealing than the initial number when considering metabolic acidosis.
Another important cause of a reduced or unexpectedly average result is paraproteinemia. Abnormal proteins can alter the blood chemistry pattern and shift the apparent balance of measured ions. In such cases, the anion gap is not a diagnosis by itself, but a hint that may prompt further workup.
When interpreting low or normal results, look at the entire clinical interpretation: albumin level, other electrolytes, pH, bicarbonate, kidney function, and the patient’s symptoms. This broader approach strengthens diagnostic interpretation and helps avoid false reassurance.
Step-by-Step Sample Calculation
Here is a simple worked example with typical laboratory values. Suppose the patient has the following:
- sodium level: 140 chloride level: 102 bicarbonate level: 18 potassium level: 4.0
Applying the usual sodium-based formula, the calculation is:
anion gap = 140 - (102 + 18)This yields an anion gap of 20. If the lab’s expected range is lower than that, this may indicate a elevated anion gap. When the patient also has low serum albumin, the next step is albumin correction to determine the albumin-corrected anion gap.
Now assume the albumin is reduced. Following applying the appropriate anion gap correction, the corrected value may be even higher, revealing a more significant metabolic problem than the unadjusted number suggested. That is why the Anion Gap Calculator is a highly practical diagnostic aid: it simplifies the math while preserving the clinical meaning.
That sample calculation also shows how the result connects to the rest of the evaluation. A high gap with low bicarbonate can support concern for metabolic acidosis, while the underlying cause may be lactate buildup, ketone-related acidosis, renal failure, toxic alcohol ingestion, or salicylates. The calculator does not identify the cause, but it assists in narrowing the differential.
Frequently Asked Questions About Adjusted Anion Gap Results
What exactly is a corrected anion gap and why is it used?
The albumin-corrected anion gap is the usual anion gap adjusted for low serum albumin. It is used because hypoalbuminemia can make the uncorrected value look falsely normal. The correction enhances clinical interpretation and more accurately shows the patient’s true acid-base balance.
How do you determine the anion gap with albumin correction?
Start with the usual anion gap formula using serum sodium, serum chloride, and serum bicarbonate. Then add an albumin correction based on the measured serum albumin. The exact method may vary by institution, so the calculator should follow the same reference range and formula used by the lab or clinical setting.
What can indicate a high anion gap?
A high anion gap commonly suggests extra acids in the blood, such as in lactic acidosis, ketoacidosis, renal failure, or exposure to toxic alcohols or salicylates. It is a key clue in the evaluation of metabolic acidosis, but it should be interpreted with the rest of the laboratory results and the patient’s symptoms.
Can a normal anion gap still mean a serious problem?
Yes. A normal anion gap does not always rule out clinically important illness. Hypoalbuminemia can hide a true gap, and a lab error can also distort the result. In addition, a patient may have another type of metabolic problem that requires broader acid-base evaluation and clinical review.
When should an anion gap result be reviewed by a clinician?
Any unexpected result should be reviewed when it does not fit the patient’s condition, especially if there is metabolic acidosis, altered mental status, kidney dysfunction, suspected poisoning, or significant electrolyte imbalance. The result is best used as a diagnostic aid within overall patient assessment, not as a standalone answer.