What the Anion Gap Assesses
The anion gap is a useful way to evaluate the relationship between electrolytes that are measured in routine blood testing and those that are not measured directly. Clinically, it assists in assessing acid-base balance and can suggest an acid-base disorder, especially when a patient may have an electrolyte imbalance.
In plain language, the anion gap compares the main measured cations and anions in the blood. The result helps identify whether there are excess unmeasured anions, which often occurs in metabolic acidosis. That makes it a useful screening metric and a reliable diagnostic tool in routine lab values review.
An anion gap calculator is designed to make this process fast and reliable. Instead of calculating by hand, you enter the relevant serum electrolyte values and get an instant formula result. This can support faster clinical interpretation and help inform further evaluation when the anion gap value is abnormal.
Formula and Calculation
The common anion gap calculation relies on sodium, chloride, and bicarbonate:
Anion gap = Sodium - (Chloride + Bicarbonate)
In most routine calculations, blood sodium is the main positive value, while blood chloride and blood bicarbonate are the amounts removed from it. Because bicarbonate is a major buffer, the bicarbonate level strongly affects the final number and often shows the body’s current acid-base status.
As an example, if serum sodium is 140, serum chloride is 104, and serum bicarbonate is 24, the calculation is:
140 - (104 + 24) = 12
That anion gap value is then measured with a reference range to help determine whether the result is within range or outside range. A correctly interpreted result can be especially valuable during a acidosis workup, where identifying the pattern can narrow the possible cause.
While the equation is easy to use, the meaning of the result depends on the overall clinical context. A single number does not diagnose a condition by itself, but it can signal when further testing is needed.
Using the Anion Gap Calculator
Using an anion gap calculator is simple when you have the correct calculator input values. Provide the three key lab measurements: serum sodium, serum chloride, and serum bicarbonate. The tool then runs the anion gap formula and delivers the calculated value instantly.
To obtain the most accurate result, use current and matching lab measurements from the same blood chemistry panel. If values are entered from different draws, the calculation may be less reliable. Since the anion gap is based on lab data, good input quality matters for accurate lab test interpretation.
- Enter serum sodium in the first field. Enter serum chloride in the second field. Enter serum bicarbonate in the third field.
Once you calculate anion gap, compare the result with the expected normal anion gap range used by the laboratory or clinical setting. A somewhat different reference range may apply depending on the method used by the lab. This is why the calculator should assist, not replace, professional review of lab values.
When interpreting the output, pay attention to whether the formula result suggests a high anion gap, a low anion gap, or a value in the expected range. That classification helps guide next steps in evaluating possible acid-base or metabolic concerns.
Typical Anion Gap Values and Meaning
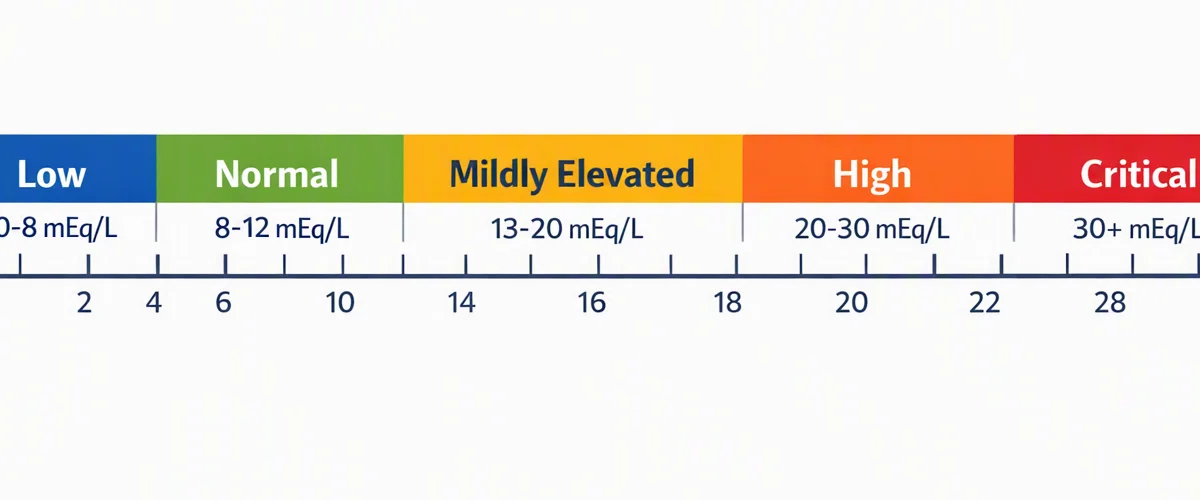
The reference range for anion gap can vary somewhat by lab, but many clinical references treat values near 8 to 12 mEq/L to be common when not adjusted for albumin. Some laboratories may use a different lab range, so it is important to assess the value alongside the reported lab standards.
A within-normal-range anion gap generally implies that the balance between measured electrolytes and unmeasured ions is not significantly altered. However, a normal result does not eliminate all disorders. Some conditions can still be present even when the anion gap is normal, especially if the problem is unrelated to excess unmeasured anions.
A elevated anion gap often signals excess acids in the blood and is commonly associated with metabolic acidosis. A low anion gap is less common but can be important because it may point to low albumin, lab issues, or unusual protein changes. Both abnormal patterns require attention in a full clinical assessment.
In practice, the anion gap is one part of the larger picture. A number that appears just beyond the expected range should be reviewed with symptoms, history, medications, and other lab findings rather than interpreted alone.
Frequent Causes of a Elevated Anion Gap
A elevated anion gap usually means there are extra unmeasured anions in the blood, often because acids are piling up. This pattern is a key sign in metabolic acidosis and often leads to a broader metabolic acidosis workup.
One common cause is elevated lactic acid, which can occur when the body generates too much lactate or cannot remove it effectively. Another important cause is ketone-related acidosis, which may develop when ketones build up during insulin deficiency, prolonged fasting, or other metabolic stress.
Impaired kidney function is another major cause because the kidneys may be unable to eliminate acids efficiently. As waste acids accumulate, the anion gap value can climb. Depending on the situation, the abnormal result may be accompanied by other changes in serum electrolyte values and a low bicarbonate concentration.
Other causes can occur as well, but these are among the most usual and important causes. When the calculator shows a high result, the pattern should be assessed in combination with the patient’s symptoms, medications, and the broader blood chemistry test.
Frequent Causes of Low Anion Gap
A low anion gap is often less common than a high one, but it may still be clinically meaningful. A common cause is hypoalbuminemia, because albumin is a major negatively charged protein in circulation. When albumin drops, the measured gap may also decrease.
Lab error should also be checked for, especially if the result does not fit the clinical picture. Rechecking the sample or reviewing sample handling can help determine whether the value is real or due to an analytical issue.
Paraproteinemia is another key cause. In this condition, abnormal proteins can change the balance of measured and unmeasured ions, how to interpret delta ratio altering the calculated result. Because of that, a low result may sometimes prompt additional testing for protein abnormalities.
While a low result is often missed, it may signal an underlying problem worth evaluating. It is best understood alongside the rest of the blood chemistry panel and the patient’s overall health.
Modified Anion Gap and Albumin Correction
Because albumin has a substantial effect on the anion gap, the raw number may underestimate the true acid burden when albumin is low. This is why clinicians sometimes use a corrected anion gap with albumin correction.
This adjustment matters because albumin helps with protein binding and has a negative charge. When albumin decreases, the measured gap can seem lower even if there is still meaningful acidosis. Correcting the value can provide a more accurate picture of acid-base status.
A corrected result is especially helpful when evaluating a possible acid-base disorder or when the patient has conditions associated with hypoalbuminemia. The goal is to not overlook a hidden high anion gap simply because the raw number seems closer to normal.
Not every case requires correction, but it should be considered whenever albumin is below normal or when the clinical picture and the calculated result do not match. In that setting, the corrected anion gap can improve clinical interpretation and promote more accurate decision-making.
When to Pursue Medical Evaluation
An abnormal anion gap is not always an emergency, but it should not be overlooked. If a person has alarming symptoms such as rapid breathing, confusion, severe weakness, vomiting, dehydration, or marked illness, medical evaluation may be needed quickly.
Because a high value can signal an important underlying problem, a clinician may request a blood chemistry panel along with other tests to determine the cause. This is especially true when there is concern for metabolic acidosis, renal failure, or another serious condition.
Seek emergency evaluation if symptoms are serious, worsening, or associated with fainting, difficulty breathing, altered mental status, or signs of severe dehydration. The calculator is a practical screening step, but it does not substitute for urgent care when the situation suggests a medical emergency.
For milder concerns, follow-up testing and clinician review can help determine whether the result was transient, related to lab error, or part of a larger pattern that needs treatment.
Frequently Asked Questions
How do you compute anion gap from sodium, chloride, and bicarbonate?
Use the anion gap formula: sodium minus the sum of chloride and bicarbonate. In other words, anion gap = sodium - (chloride + bicarbonate). An anion gap calculator makes this simple by letting you enter the serum sodium, serum chloride, and serum bicarbonate values directly.
What is the normal range for anion gap?
The normal range varies by laboratory, but many references place it around 8 to 12 mEq/L. Always compare the result to the lab’s own reference range because methods and reporting standards can differ. A result inside the expected range is often considered a normal anion gap.
What does a high anion gap?
A high anion gap usually suggests excess acids or unmeasured anions in the blood. Typical causes include metabolic acidosis, lactic acidosis, ketoacidosis, and renal failure. The result should be interpreted in the light of symptoms, other lab values, and the overall acid-base balance.
What can lead to a low anion gap?
A low anion gap can be caused by hypoalbuminemia, lab error, or paraproteinemia. Low albumin is particularly common because albumin contributes negative charge in the blood. If the result is surprising, repeating the test and reviewing the full blood chemistry panel can help clarify the cause.
Should anion gap be corrected for albumin?
Yes, it often should be evaluated when albumin is low. The corrected anion gap can offer a more accurate picture because albumin affects the measured value through protein binding and its negative charge. Albumin correction is most useful when evaluating an abnormal result during an acid-base disorder assessment.