What the Anion Gap Is Measured
The anion gap is a derived value that enables clinicians evaluate acid-base balance and detect unmeasured anions in the blood. It is most often calculated from a basic electrolyte panel using serum sodium, serum chloride, and serum bicarbonate. In practical terms, the anion gap is a tool for laboratory interpretation that can indicate metabolic acidosis even before the full cause is known.
The calculation reflects the difference between the main measured cations and anions in serum. Because the body contains many charged particles that are not directly measured, the anion gap calculation can uncover hidden acids from acid accumulation, toxins, or organ dysfunction. A higher-than-expected value often points to a pathologic process such as high anion gap metabolic acidosis, while a normal value may lead clinicians to consider other causes of illness.
An anion gap calculator automates this step and lowers the chance of arithmetic mistakes during clinical assessment. In a toxicology setting, that efficiency matters because the result may trigger toxicology screening, more urgent lab testing, or immediate treatment. Although the number itself is simple, its interpretation can be very important.
How Toxic Ingestion Can Raise the Anion Gap
Poisoning is often a common cause of increased anion gap because many poisons produce acids directly or alter metabolism in ways that boost acid production. In these cases, the body accumulates unmeasured anions that widen the calculated gap. This pattern is key to identifying high anion gap metabolic acidosis in a poisoning workup.
Some exposures, especially toxic alcohols, are well-known causes. Methanol and ethylene glycol are metabolized into acidic compounds that lead to metabolic acidosis. Soon after ingestion, the osmolar gap may be elevated before the anion gap rises, while subsequently the anion gap can become markedly abnormal as toxic metabolites accumulate. This timing issue is one reason why both values are useful in clinical assessment.
Other poisonings can raise the gap through lactic acidosis, impaired tissue oxygen delivery, seizures, shock, or mitochondrial dysfunction. Salicylate toxicity can also produce complex changes in acid-base balance, sometimes combining respiratory alkalosis with metabolic acidosis. The underlying process may involve increased lactate, impaired clearance, or the addition of other acids into circulation.
In many cases, the anion gap is not the diagnosis itself but a diagnostic signal. It helps clinicians recognize that something is driving acid-base abnormality and may warrant immediate toxicology evaluation. This makes it especially useful when symptoms are nonspecific, such as nausea, altered mental status, tachypnea, or unexplained systemic toxicity.
How to Use an Anion Gap Calculator
An anion gap calculator typically needs only the values from an electrolyte panel: serum sodium, serum chloride, and serum bicarbonate. The common formula is sodium minus chloride, then minus bicarbonate. The resulting figure estimates the difference between measured cations and anions and is useful for identifying for hidden acid load.
For toxic ingestion, calculator use should go beyond the raw number. A careful review of albumin is important because low albumin lowers the measured gap and can hide clinically meaningful abnormalities. This is why many clinicians calculate a corrected anion gap. Albumin correction improves sensitivity when evaluating possible poisoning, especially in hospitalized or critically ill patients with hypoalbuminemia.
Using the calculator in sequence can promote timely decision-making:
- Confirm the electrolyte panel values are current and internally consistent. Calculate the raw anion gap. Check albumin and determine the corrected anion gap if needed. Measure the result with the expected diagnostic threshold for concern. Interpret the result alongside symptoms, history, and other studies.
This process improves laboratory interpretation and helps align the gap with the broader clinical picture. For example, a patient with suspected ingestion may have an only mildly elevated raw gap but a clearly abnormal corrected value. That distinction can shift the level of concern for toxic ingestion and guide next steps in urgent management.
Common Toxic Sources of Increased Anion Gap
Several toxic exposures are often associated with raised anion gap and elevated anion gap metabolic acidosis. The key include methanol, ethylene glycol, salicylates, and conditions with increased ketones. Each creates a somewhat more different pattern, but each one can be associated with acid base derangements significant enough to require rapid recognition.
Methanol is metabolized into formic acid, which results to severe acidosis and can also cause visual symptoms. Ethylene glycol is converted to glycolic and oxalic acids, which may harm the kidneys and contribute to renal failure. The presence of crystals, worsening creatinine, or neurologic changes can support suspicion, but the anion gap often provides the first laboratory clue.
Salicylates can cause a mixed pattern with early respiratory alkalosis and later metabolic acidosis. The anion gap clinical significance acid-base picture may be unclear unless the clinician considers toxicology. Ketones are another major source of elevated gap, especially in diabetic ketoacidosis, alcoholic ketoacidosis, or starvation-related states. In these settings, ketoacidosis and the buildup of ketone bodies directly contribute to the abnormality.
It is also important to remember that toxins may act indirectly. Some exposures cause vomiting, hypoperfusion, seizure activity, or hypoxia, which can drive lactic acidosis. Others impair metabolism and increase acid production without obvious early symptoms. A calculated gap can therefore be a valuable bridge between nonspecific symptoms and a targeted toxicology diagnosis.
How to Read Findings in Clinical Context
The anion gap should not ever be read on its own. A elevated result suggests metabolic acidosis, but the subsequent step is to determine whether the pattern matches a specific acid-base disorder. In toxic ingestion, the most important supporting studies often include the osmolar gap, an arterial blood gas, and a repeat electrolyte panel to verify trends.
The osmolar gap can be especially helpful initially in suspected exposure to toxic alcohols. A increased osmolar gap suggests unmeasured osmotically active substances, while a increasing anion gap indicates accumulation of acidic metabolites. Together, these findings support the suspicion for methanol or ethylene glycol poisoning.
An arterial blood gas offers direct information about pH, bicarbonate, and respiratory compensation. It helps determine whether there is severe acidemia, whether ventilation is compensating appropriately, and whether a mixed disorder is present. In a patient with poisoning, that data can guide airway, ventilation, and antidotal decisions.
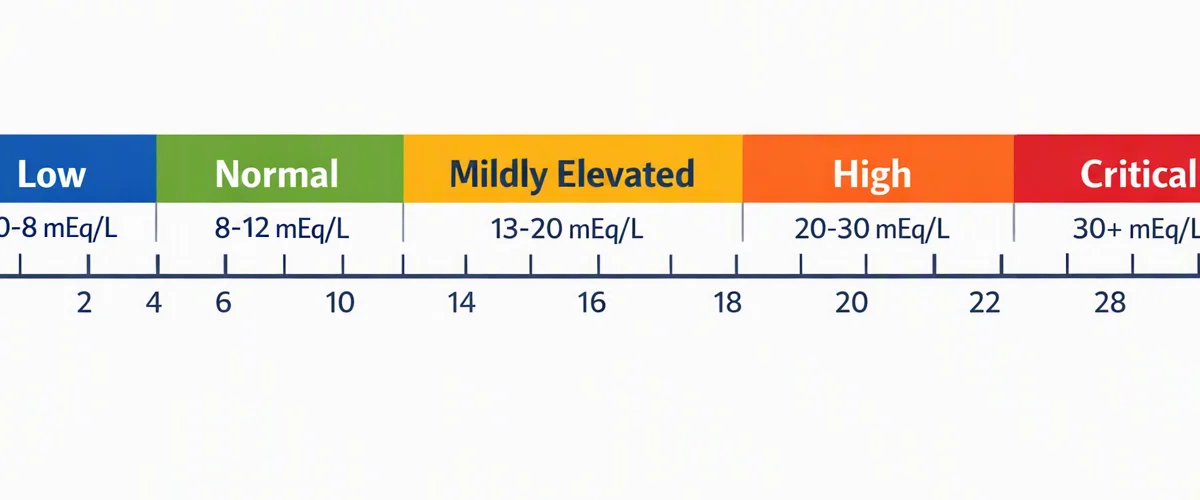
Context matters equally with numbers. Tachypnea, visual complaints, altered mentation, abdominal pain, renal injury, or hemodynamic instability all increase concern for systemic toxicity. When the lab pattern aligns with and the history is uncertain, the combination of anion gap, osmolar gap, and blood gas findings can justify immediate toxicology consultation and treatment.
Constraints and Pitfalls of Anion Gap Calculation
Although useful, the anion gap has significant limitations. Among the most frequent is hypoalbuminemia. Since albumin is a major unmeasured anion, low levels can make a truly abnormal gap appear normal. This is why a corrected anion gap is so crucial in severely ill or malnourished patients.
Another pitfall is mixed acid-base disorders. A patient may have both a high anion gap metabolic acidosis and a concurrent metabolic alkalosis or respiratory disturbance, which can hide severity. This is where the delta gap becomes important. The delta gap compares the change in the anion gap to the change in bicarbonate and can detect hidden alkalosis or additional acid-base processes.
Lab error is another concern. Hemolysis, specimen issues, transcription problems, or delays in processing can distort the values used in the calculation. If the result does not match the clinical picture, repeating the test may be necessary before making major decisions. That caution is especially relevant when a poisoning workup is already underway.
In the end, a normal anion gap does not fully exclude toxic exposure. Some ingestions are early in their course, some are partially treated, and some produce mixed patterns. For that reason, clinicians should treat the calculator as a decision support tool rather than a standalone rule-out test. The best practice is to combine laboratory interpretation with symptoms, exposure history, and serial reassessment.
If an Elevated Anion Gap Calls for Immediate Action
An increased anion gap in the setting of suspected poisoning may indicate a critical emergency. If there is altered mental status, severe acidemia, visual symptoms, kidney injury, or hemodynamic instability, the patient needs emergency evaluation right away. Prompt communication with the poison center can help identify likely exposures and inform antidotal or supportive treatment.
Prompt action becomes even more important when toxic alcohols are suspected because delays can worsen outcomes. In certain situations, hemodialysis may be recommended to remove the toxin and correct severe acidosis. This is especially relevant for methanol and ethylene glycol poisoning, as well as for profound metabolic derangement that is not responding to initial measures.
Clinicians should also think beyond the number itself. A patient with a steadily climbing gap, worsening pH, or supportive osmolar gap findings may need sodium chloride bicarbonate anion gap prompt treatment even before confirmatory levels return. Early antidotal therapy, aggressive supportive care, and close reassessment are often central to urgent management.
If there is any uncertainty, the safest course is to step up care. Severe high anion gap metabolic acidosis can deteriorate fast, and a delayed response may allow more toxin metabolization and tissue injury. In practice, anion gap calculator is most valuable when it helps identify the point at which observation is no longer enough and urgent intervention is needed.
Common Questions
What is considered a normal anion gap?
The anion gap reference range varies by the laboratory testing method, but a common normal AG is often roughly the low and mid teens. Because multiple analyzers and reference intervals can vary, the local lab range should be used when available. In toxicology, even a borderline increase can matter if symptoms or exposure history suggest poisoning.
What effect does toxic ingestion have on the anion gap?
Poisonous ingestion can increase the anion gap by adding acids to the blood, leading to acid retention, or disrupting metabolism so that acids such as lactate and ketone bodies collect. This leads to high anion gap metabolic acidosis. Exposures like methanol, ethylene glycol, and salicylates are important examples.
Which toxic alcohols cause a high anion gap?
The primary toxic alcohols associated with a high anion gap are methanol and ethylene glycol. They form acidic metabolites that cause metabolic acidosis. A elevated osmolar gap may be seen early, followed by a progressively higher anion gap as the metabolism progresses.
Why should albumin be used to correct the anion gap?
Serum albumin is a important unmeasured anion, so reduced levels can decrease the observed gap and mask clinically significant disease. Applying a adjusted anion gap improves interpretation in patients with hypoalbuminemia. It is especially valuable in critical illness, where the raw number may underestimate the severity of a toxicologic problem.
When does an elevated anion gap require urgent care?
Urgent attention is needed when an elevated anion gap occurs with features of poisoning, confusion, fast breathing, persistent vomiting, vision changes, kidney injury, or declining illness. As these can signal dangerous systemic toxicity, the patient should get emergency evaluation. If a toxic exposure is possible, contacting a poison center right away is advisable, and hemodialysis may be needed in advanced cases.