What’s the anion gap?
The anion-gap value is a helpful method to assess electrolytes and understand the difference between measured and unmeasured anions in the blood. It is usually calculated from a serum chemistry panel and assists clinicians focus the differential diagnosis for acid-base disorders, especially metabolic acidosis.
From a physiology standpoint, the anion gap shows the difference between the main measured cations and anions in serum. Because routine testing does not directly measure every ion, the calculated value estimates the amount of unmeasured ions present. This makes the anion gap a valuable tool for clinical interpretation and laboratory assessment when evaluating an acid-base disturbance.
Medical students often initially encounter the anion gap as part of a broader serum chemistry or electrolyte panel. It is especially important because a change in the gap can indicate a hidden metabolic derangement anion gap clinical significance even when the pH has not yet been reviewed. In other words, the anion gap is not just a number; it is a pointer to the underlying acid-base balance.
How to Calculate the Anion Gap
The formula for the anion gap is commonly written as:
Anion gap = sodium − (chloride + bicarbonate)In this formula, sodium is the chief measured cation, while chloride and bicarbonate are the measured anions. An anion gap calculator makes easy this calculation from the lab values you enter, helping lower arithmetic errors during a hectic clinical routine.
It is simple to use the calculator:
- Type in the serum sodium value. Enter the serum chloride value. Type in the serum bicarbonate value. The calculator gives the anion gap and often shows whether it is elevated or within the expected reference interval.
For example, if sodium is 140, chloride is 104, and bicarbonate is 24, the anion gap is 12. In many laboratories, this is anion gap lactic acidosis regarded as normal. The exact interpretation depends on the lab’s reporting method and local reference range, so students should always compare the result with the values provided by the institution.
It is important to understand the formula because the result is only as reliable as the underlying data. If any value is inaccurate due to a measurement error, the calculated anion gap may be misleading. That is why clinicians should always interpret the output in the context of the broader electrolyte disorder and the patient’s clinical picture.
Normal Values and Albumin Correction
A normal anion gap is usually set by the laboratory’s reference range, which may vary depending on the analyzer and whether potassium is included in the equation. A common non-potassium reference interval is roughly 8 to 12 mEq/L, but this should not replace the local lab standard.
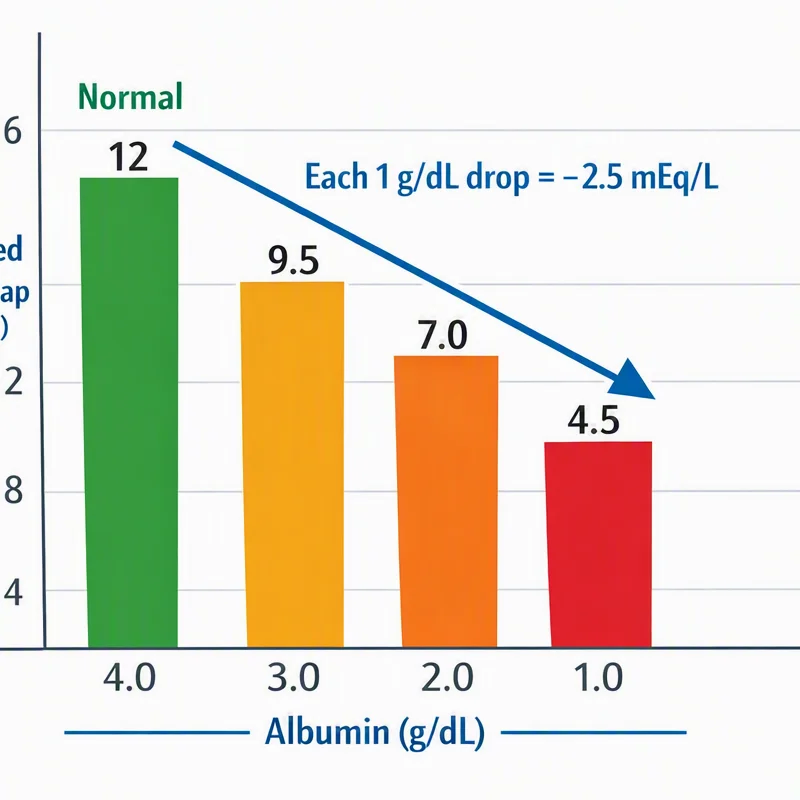
One of the most important adjustments in real practice is the effect of albumin. Because albumin is a major unmeasured anion, low albumin can make the anion gap appear falsely low or normal even when an acid load is present. This is why albumin correction is often important for accurate interpretation.
A practical way to think about it: when albumin falls, the measured anion gap falls too, because fewer negatively charged proteins are contributing to the total. A adjusted value helps identify an elevated gap that might otherwise be missed. In many teaching settings, a commonly used correction is to add approximately 2.5 mEq/L to the anion gap for every 1 g/dL decrease in albumin below 4 g/dL. However, students should follow local teaching standards and institutional methods.
This is especially important in hospitalized patients, where hypoalbuminemia is common. Without albumin correction, clinicians may underestimate the severity of acid-base acidosis. A apparently normal result on an anion gap calculator does not always mean the acid-base picture is normal.
Medical Assessment of an High Anion Gap
An elevated anion gap points to the existence of extra acids or certain unmeasured ions in the serum. This result is classically seen in high anion gap metabolic acidosis, a major topic in acid-base medicine. In this scenario, the body builds up acids, and bicarbonate is depleted as buffering happens.
Common causes include lactic acidosis, ketoacidosis, and uremia. Each has a separate pathophysiology, but all can produce a raised gap:
- Lactic acidosis: increased lactate from tissue hypoperfusion, sepsis, severe exercise, or impaired lactate clearance. Ketoacidosis: build-up of ketone bodies in diabetic, alcoholic, or starvation states. Uremia: retention of acids in advanced kidney failure, adding to the burden of unmeasured anions.
When the gap is high, the next step is not merely to label the disorder. Students should ask why the acid is present, how marked the derangement is, and whether there are further abnormalities. The anion gap helps with diagnostic approach, but it is only one piece of the puzzle.
For example, a patient with vomiting, altered mental status, and high glucose may have ketoacidosis. Another patient with hypotension and rising lactate may have lactic acidosis. A third patient with renal failure and elevated creatinine may have uremia. In each case, the same calculator output requires distinct clinical interpretation.
Causes of a Typical Anion Gap Metabolic Acidosis
Not every metabolic acidosis causes an high gap. Normal anion gap metabolic acidosis, also called non-anion gap metabolic acidosis, occurs when bicarbonate is lost or chloride rises to maintain electroneutrality. In this pattern, the anion gap remains in the normal range even though the patient is acidotic.
The chief causes are diarrhea and renal tubular acidosis. With diarrhea, the gastrointestinal tract loses bicarbonate, producing loss of bicarbonate and a drop in serum bicarbonate. With renal tubular acidosis, the kidneys fail to recover bicarbonate appropriately or fail to excrete acid, leading to a persistent acid-base problem despite preserved or only mildly impaired kidney function.
In practice, the body often responds by elevating chloride, which is why hyperchloremic acidosis is another common way to describe this pattern. Students should understand that the absence of an elevated anion gap does not mean there is no significant acid-base disturbance. It simply points toward a distinct mechanism.
A step-by-step evaluation should include the history, medication use, kidney function, gastrointestinal losses, and the broader electrolyte pattern. This kind of diagnostic approach is better than relying on a calculator result alone.
Step-by-Step Approach to Acid-Base Disorders
To analyze any acid-base disturbance, medical students should work in a stepwise order rather than going straight to one number. The process starts with the ABG, then moves to serum electrolytes, then to the anion gap, and finally to compensation and mixed disorders.
A practical stepwise method is:
- Check the arterial blood gas for pH, CO2, and bicarbonate. Determine whether the primary problem is metabolic or respiratory. Apply the anion gap to divide metabolic acidosis as high gap or normal gap. Evaluate the compensatory response to see whether respiratory response is appropriate. Check the delta analysis if the anion gap is elevated to look for additional disorders.
The delta analysis helps identify whether the rise in the anion gap is proportional to the fall in bicarbonate. If the change does not fit expectations, a combined acid-base disorder may be present. This matters because a patient can have more than one process at the same time, such as high anion gap metabolic acidosis plus metabolic alkalosis from vomiting.
The compensatory response should always be assessed because the body responds predictably to primary metabolic disturbances. For example, in metabolic acidosis, the respiratory system usually lowers CO2 through hyperventilation. If compensation is absent or excessive, another process may also be occurring.
This framework turns the anion gap calculator into more than a formula tool. It becomes part of a broader structured assessment of the patient’s acid-base status.
Typical Pitfalls In Using an Anion Gap Calculator
One common pitfall is failing to account for albumin. As hypoalbuminemia decreases the apparent gap, students may fail to identify a clinically important high-gap state unless they apply the corrected anion gap. This is especially relevant in critically ill patients, where low albumin is common.
One other problem is relying on the calculator without checking the actual lab values. The anion gap is only useful if sodium, chloride, and bicarbonate are reliable and comparable. A single transcription error can change the result enough to affect the interpretation.
Students also sometimes forget that a “normal” value does not rule out disease. A patient with severe hypoalbuminemia may have a deceptively normal result even in the presence of significant acid generation. Likewise, a mixed acid-base disorder can hide behind a seemingly straightforward number.
Additional mistakes include:
- Failing to check the laboratory’s reference interval. Neglecting the role of measurement error in electrolyte testing. Neglecting to relate the result with the patient’s symptoms and diagnosis. Thinking all metabolic acidosis is high gap.
The best habit is to view the calculator as an assistant, not a replacement for thinking. Accurate interpretation requires integrating the result with the clinical story, blood gas analysis, and the broader metabolic context.
Review Scenarios for Students in Medicine
Clinical case 1: The patient has a serum sodium of 138, serum chloride of 100, and serum bicarbonate of 14. The anion gap is 24, which is elevated. This pattern clearly suggests high-gap metabolic acidosis. The next step is to consider causes such as lactic acidosis, diabetic ketoacidosis, and uremia, then correlate with vitals, glucose, creatinine, and lactate.
Case 2: The patient presents after several days of marked bowel losses. Serum sodium is 140, serum chloride is 112, and serum bicarbonate is 18. The anion gap is 10, and that is within the expected range. This fits with non-gap metabolic acidosis caused by loss of bicarbonate. The higher chloride level supports a hyperchloremic pattern.
Example 3: A patient with advanced kidney disease has sodium 135, chloride 98, and bicarbonate 15. The anion gap is 22, pointing to retained acids and possible uremia. If albumin is low, the albumin-adjusted calculation may reveal an even higher corrected value. That corrected value provides better clinical interpretation than the raw number alone.
Clinical case 4: A patient with type 1 diabetes has sodium 130, chloride 95, bicarbonate 8, and signs of dehydration. The result points to ketoacidosis. In this setting, the anion gap calculator helps confirm the presence of a high-gap metabolic process, but treatment decisions depend on the full clinical picture, including glucose, ketones, potassium, and blood gas analysis.
These cases show that the calculator is only a starting point. Its real value comes from linking the result to pathophysiology, diagnosis, and management.
FAQs
Why use an anion gap calculator?
An Anion Gap Calculator is designed to calculate the difference between measured cations and anions from routine labs. It helps evaluate acid-base acidosis, identify unmeasured acids, and guide the diagnostic approach to acid-base problems. It is particularly useful for identifying high anion gap metabolic acidosis and deciding whether albumin correction is needed.
How is calculated the anion gap using lab values?
Follow the anion gap equation: sodium minus chloride and bicarbonate combined. Written as a formula, it is sodium − (chloride + bicarbonate). Enter the values into an anion gap calculator to minimize arithmetic mistakes, then check the result with the local reference interval.
What represents a normal anion gap range?
The reference range varies with the laboratory method and whether potassium is included. A number of labs use a non-potassium range around 8 to 12 mEq/L, but students should always use the institution’s stated reference interval. A “normal” value must also be interpreted in light of albumin and the broader clinical picture.
Why is it corrected the anion gap for albumin?
You adjust for albumin because it is a major unmeasured anion. In hypoalbuminemia, the measured gap may seem falsely low or normal, which can hide a true acid-base problem. Albumin correction yields a more accurate corrected value and improves clinical interpretation.
What can cause a high anion gap metabolic acidosis?
Major causes include lactic acidosis, ketoacidosis, and uremia. These conditions raise unmeasured ions and lower bicarbonate, producing high anion gap metabolic acidosis. A detailed review of the arterial blood gas, electrolytes, kidney function, glucose, and lactate helps verify the cause.