An anion gap calculator is a helpful diagnostic tool used to assist clinicians and patients calculate anion gap values and aid kidney assessment when an acid-base disorder is suspected. It is especially important useful when reviewing lab values from an electrolyte panel or a basic metabolic panel, because the result can point toward metabolic acidosis, a common metabolic derangement seen with impaired kidney function.
In kidney disease, especially chronic kidney disease and acute kidney injury, the body may struggle to clear acids effectively. That can alter serum electrolytes and shift the balance between sodium, chloride, and bicarbonate. A carefully interpreted anion gap result can help determine the likely cause of acidosis and support further laboratory testing.
What the Anion Gap Assesses
The anion gap shows the difference between lab-measured positively charged and negatively charged electrolytes in the circulation. It is typically determined using sodium, chloride, and bicarbonate, and sometimes includes potassium depending on the calculation formula used.
While the body contains many ions, standard blood tests do not capture every charged particle directly. The anion gap aids in estimate the amount of unmeasured anions, which is useful for assessing acid-base balance. In practice, this provides clinicians a simple way to screen for hidden acids that may be rising in the bloodstream.
For kidney disease evaluation, this matters because the kidneys play a central role in acid excretion and bicarbonate regulation. When renal clearance declines, the pattern of serum electrolytes can reveal important clues about underlying renal impairment.
The key components are:
- Sodium, the main measured cation Chloride, the main measured anion Bicarbonate, which helps buffer acid in the blood Potassium, which may or may not be included in the formula
Because this is a calculation based on routine lab values, the anion gap is often one of the first tools used to evaluate an unexplained acid-base disorder.
How the Anion Gap Calculator Operates
An anion gap calculator applies a straightforward formula with values from a blood chemistry test. In most cases, the calculation is:
Anion gap = sodium − (chloride + bicarbonate)
Some versions of the formula also include potassium, but many clinical settings omit it because the contribution is relatively small. For this reason different calculators may produce slightly different results. The most important step is to use the same method consistently when you interpret anion gap trends over time.
The calculator is particularly useful when values come from a recent basic metabolic panel or broader serum electrolytes test. A clinician may use the result to identify whether the patient has a high anion gap metabolic acidosis, a normal anion gap metabolic acidosis, or a low gap pattern that suggests another issue.
In clinical interpretation, the number itself is only part of the picture. The context matters: symptoms, kidney function, serum bicarbonate, and other markers such as serum creatinine and blood urea nitrogen help determine what the calculation really means.
Using an anion gap calculator can be very useful when reviewing:
- Inexplicable low bicarbonate Suspected acid retention in kidney disease Variations in electrolytes during illness Likely causes of metabolic acidosis
Why the Anion Gap Matters in Kidney Disease
In chronic kidney disease, the kidneys gradually lose their ability to remove acid and regenerate bicarbonate. This can lead to metabolic acidosis, which may show up as a rising or atypical anion gap. As kidney function worsens, acid retention becomes more common, making the anion gap a useful common NAGMA causes marker of altered metabolic status.
In acute kidney injury, the problem may occur suddenly. A sudden decline in filtration can trigger rapid changes in serum electrolytes and acid handling. That makes the anion gap calculator a reliable way to assess whether the patient’s acidosis is probably related to kidney failure or another acidosis causes category.
In advanced renal dysfunction, renal impairment may worsen uremia, which can raise unmeasured acids in the blood. This is why an elevated gap is often reviewed alongside blood urea nitrogen and serum creatinine. Together, these lab results can point to worsening kidney function and a broader metabolic derangement.
The anion gap does not diagnose kidney disease by itself. Instead, it helps support the overall clinical interpretation of the acid-base picture. When paired with the patient’s history, symptoms, and other laboratory testing, it helps clarify whether the pattern is consistent with kidney-related acidosis or another disorder.
How to Interpret Elevated, Normal, and Reduced Anion Gap Results
Reading the anion gap requires knowing the relationship of acid-base balance. A result may be elevated, within normal range, or low, and each pattern indicates different possibilities.
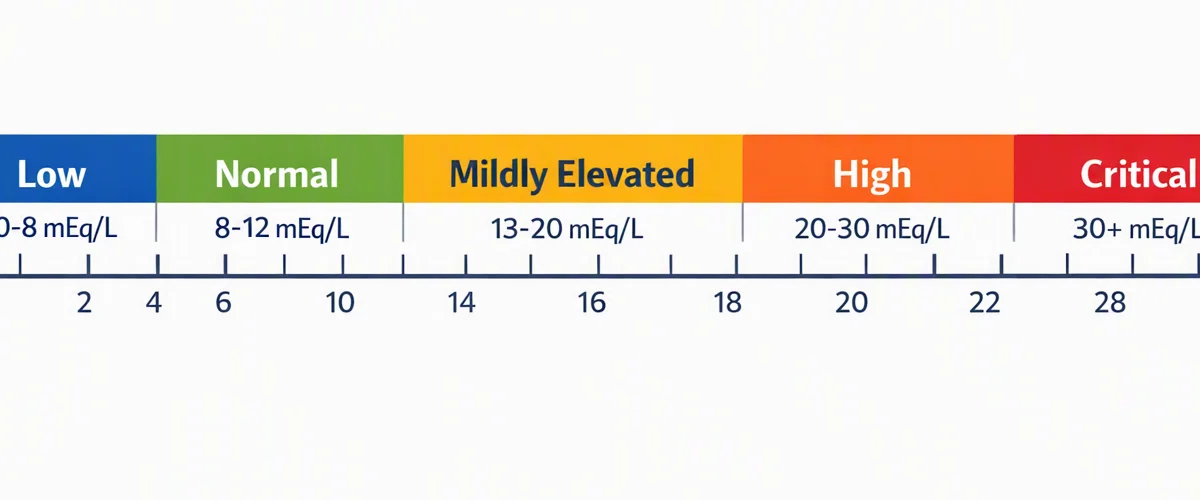
A high anion gap often indicates there are extra hidden acids in the blood. This pattern is frequently observed in high anion gap metabolic acidosis, which may occur with kidney disease, lactic acidosis, ketoacidosis, or toxic ingestions.
A normal anion gap does not exclude acidosis. As a result, normal anion gap metabolic acidosis can happen when bicarbonate is lost and chloride rises to compensate. This can be seen in certain renal tubular disorders or other conditions that affect acid handling without causing a large increase in unmeasured acids.
A low anion gap is less common, but it can point to low albumin, lab artifact, or other unusual conditions. Because the gap is influenced by many factors, it should always be reviewed alongside the full electrolyte pattern and the patient’s clinical picture.
In practical terms, interpretation includes:
- High anion gap: think added acids or reduced acid clearance Normal anion gap: think bicarbonate loss or chloride retention Low anion gap: consider protein changes, analytical issues, or uncommon causes
No matter the pattern, the goal is to determine the underlying acid-base disorder and whether the abnormality is driven by kidney-related changes, another metabolic condition, or a testing issue.
Common Causes of Elevated Anion Gap in Kidney Disorders
A number of conditions can elevate the anion gap in patients with kidney disease. The main cause is uremia, which occurs when the kidneys fail to eliminate acid waste products. As acid accumulates, the gap rises and the patient may develop severe metabolic acidosis.
Lactic acidosis is another major cause. It can occur when tissues do not receive enough oxygen or when there is major illness, infection, or poor perfusion. In a patient with renal dysfunction, lactic acid may be cleared less efficiently, making the acid-base disturbance more severe.
Ketoacidosis is also a common reason for a high gap. This may happen in uncontrolled diabetes, prolonged fasting, or other states of increased fat breakdown. Even when the primary problem is not the kidneys, reduced renal reserve can worsen the acid load.
Toxic ingestions are important to consider as well. Some substances produce acids or interfere with metabolism, leading to an elevated gap. In these cases, the anion gap calculator helps uncover a potentially fatal cause of acidosis that may otherwise be missed.
Additional points to keep in mind:
- Worsening kidney function can reduce acid clearance Blood urea nitrogen and serum creatinine may increase with renal decline A high gap may reflect several processes at the same time
A thorough review of the clinical story is essential, because a high gap anion gap clinical significance in a patient with renal impairment can signal either kidney-related acid retention or another important diagnosis occurring alongside it.
What May Reduce the Anion Gap
A low anion gap is not as common than a high one, but it still should be noted. One of the key causes is hypoalbuminemia, since albumin is a negatively charged protein that contributes substantially to the normal gap.
When serum albumin is low, the measured gap may appear artificially reduced even if the patient has a real acid-base problem. This is why the result may need albumin adjustment before interpretation. In clinical practice, hypoalbuminemia can occur in chronic illness, poor nutrition, inflammation, or protein-losing conditions.
Multiple myeloma can also lower the gap because abnormal proteins may shift the pattern of measured ions. This is less frequent than hypoalbuminemia, but it is an important consideration when the lab pattern does not fit the clinical picture.
Lab error should always be considered. Sample handling problems, instrument issues, or transcription mistakes can all distort the result. If the value seems unexpected, repeating testing is often appropriate before drawing conclusions.
Possible causes of a low gap include:
- Hypoalbuminemia Changes in albumin concentration Multiple myeloma Lab error
Because a low gap can mask a true acid-base disorder, it should not be ignored, especially in patients with kidney-related illness.
Adjusted Anion Gap and Albumin Compensation
Because serum albumin strongly impacts the anion gap, many clinicians use a corrected anion gap when albumin is abnormal. This albumin correction helps estimate what the gap would be if the albumin were in the expected range.
The concept is simple: low albumin lowers the measured gap, so adjustment helps avoid missing a true high anion gap. This matters particularly in patients with kidney disease, where malnutrition, inflammation, or chronic illness may lower albumin levels.
An albumin-adjusted interpretation is often more accurate than the raw number alone. However, the exact correction may differ by institution or calculator. Because of that, it is important to know the reference range used by the lab and the method used by the calculator.
Using a corrected value can improve clinical interpretation when the picture is unclear. For example, a patient with low albumin may have a seemingly normal gap even though acid retention is present. After adjustment, the result may better represent the underlying metabolic state.
Key points about correction:
- Low albumin can hide a true elevation Corrected anion gap can enhance diagnostic accuracy The chosen reference range should match the lab method
In short, albumin adjustment is not always required, but it is often helpful when evaluating metabolic acidosis in patients with abnormal protein levels.
Related Lab Tests to Review with the Anion Gap
The anion gap calculator is most useful when viewed alongside other tests. A basic metabolic panel provides the core values needed for the calculation and often includes clues about kidney-related acid-base problems. In many cases, a clinician will also review an arterial blood gas to better understand pH and respiratory compensation.
Serum creatinine and blood urea nitrogen are essential for measuring kidney function. If both are elevated, the result may support progressive renal impairment or an acute kidney injury episode. These tests help determine whether the abnormal gap is likely tied to impaired filtration.
Other relevant values include:
- Bicarbonate for evaluating buffering capacity Sodium and chloride for the calculation itself Potassium for more complete electrolyte assessment Serum albumin for possible correction
The arterial blood gas provides important detail about oxygenation, pH, and compensation, which can help distinguish respiratory from metabolic processes. Together, these tests provide a more comprehensive view of acid-base balance and overall metabolic status.
For a patient with abnormal results, the combination of laboratory testing can help clarify whether the issue is uremia, lactic acid buildup, ketosis, or another acid-base disturbance.
When to Seek Medical Evaluation
Anyone with abnormal lab values and concerning symptoms should seek timely medical evaluation. This is especially important when there may be acute kidney injury, severe dehydration, or worsening metabolic acidosis.
Warning signs can include nausea, vomiting, confusion, rapid breathing, weakness, or reduced urine output. Such signs do not prove kidney failure, but they can signal a significant acid-base disorder that needs prompt attention.
If the anion gap is elevated and the patient also has high serum creatinine or blood urea nitrogen, kidney-related acid retention becomes more likely. On the other hand, a typical or low gap does not exclude a problem if symptoms are progressing.
Seek out medical assessment immediately if:
- Symptoms indicate suspected severe acidosis There is suspected acute kidney injury Dehydration may be worsening renal function Results are unusual or shifting fast
As acid-base problems can evolve quickly, it is best not to rely on a single number. The anion gap calculator is a useful guide, but the final decision should come from a full clinical assessment.
Frequently Asked Questions
Why use an anion gap calculator for kidney disease assessment?
An anion gap calculator is used to help assess acid-base balance in people with kidney disease. It can show whether there is a high anion gap pattern that points to metabolic acidosis, acid retention from reduced kidney function, or another metabolic cause that needs evaluation.
How is the anion gap calculated from a basic metabolic panel?
You typically use the values for sodium, chloride, and bicarbonate from the basic metabolic panel. The common formula is sodium minus the sum of chloride and bicarbonate. Some methods also include potassium, so the exact reference range can vary by calculator and lab.
What is the significance of a high anion gap in chronic kidney disease?
In chronic kidney disease, a high anion gap may indicate accumulation of acids because the kidneys are not clearing them well. This can be part of high anion gap metabolic acidosis and may reflect uremia or another added acid burden such as lactic acidosis or ketoacidosis.
Is albumin correction needed for the anion gap?
Yes, it often should be considered when serum albumin is low. Hypoalbuminemia can make the measured gap appear falsely normal or low. A corrected anion gap with albumin correction may give a more accurate picture of the underlying acid-base problem.
Which additional lab tests should be reviewed with an unusual anion gap?
Important tests include a basic metabolic panel, ABG, blood creatinine, and urea nitrogen. Reviewing potassium, HCO3, and albumin level can also strengthen clinical assessment and assist with identifying the reason of the elevated result.