What the Anion Gap Indicates
The anion gap is a derived number that helps clinicians and patients interpret the relationship of charged particles in the blood. It is based on a common electrolytes panel, especially sodium, chloride, and bicarbonate. Because routine blood testing does not measure every charged molecule, the anion gap estimates the amount of unmeasured anions in the serum chemistry profile.
At its core, the anion gap reflects acid-base balance. When acids build up in the body, the gap can increase, signaling a possible metabolic derangement. This is why the anion gap is used as a diagnostic aid rather than a standalone diagnosis. It is a form of blood test interpretation that can reveal an anion difference even when other values seem only mildly abnormal.
The basic calculation formula checks measured cations and anions, usually using serum sodium, serum chloride, and serum bicarbonate. The result helps clinicians understand whether there is too much acid in the blood, often from acid accumulation. In practice, the anion gap is part of a larger screening tool for evaluating unexplained symptoms, abnormal lab results, and acid-base disorders.
How to Work With an Anion Gap Calculator
An anion gap calculator simplifies the calculation and helps users quickly estimate whether the result falls within the expected reference range. To use it, input the serum sodium, serum bicarbonate, and serum albumin values if the tool includes albumin adjustment. Some tools also allow direct entry of serum chloride for cross-checking the equation.
The most common formula is:
Anion gap = sodium - (chloride + bicarbonate)
Because serum albumin is a major unmeasured anion, many calculators also offer a corrected anion gap. This is important when albumin is low, since the uncorrected number may conceal clinically important acid-base abnormalities. The albumin adjustment improves the reliability of the interpretation and makes the result more useful for risk assessment.
A calculator is especially helpful when reviewing lab results during urgent or complex cases. It can signal a possible anion deficit or a pattern consistent with hidden acid-base trouble. However, the number should always be interpreted with the rest of the blood work, symptoms, and overall clinical picture.
Typical, Elevated, and Reduced Anion Gap Results
A standard anion gap often suggests the ratio between measured electrolytes is within the expected normal range. Still, a normal result does not necessarily rule out disease. Sometimes, there may also be acid buildup if the body is losing bicarbonate and replacing it with chloride, which leads to a normal anion gap finding.
A elevated anion gap metabolic acidosis shows that unmeasured acids are piling up in the blood. This result often prompts a search for the underlying source of acid. A high result is not a diagnosis by itself, but it is a useful clue that something is affecting the body's acid-base system.
A reduced anion gap is uncommon and can occur with laboratory issues, low albumin, or unusual blood chemistry patterns. Because the calculation depends on the measured electrolytes, a low result should also be reviewed carefully in context. The key point is that both high and low values require thoughtful interpretation rather than quick conclusions.
Why Hidden Metabolic Acidosis Can Be Missed
Metabolic acidosis can be subtle, especially in the beginning or when the body partially adjusts. One reason it is missed is compensatory hyperventilation, which decreases carbon dioxide and can make the patient appear just mildly unwell at first. Another reason is a mixed acid-base disorder, where one abnormal process counterbalances another and the final numbers look less striking than expected.
Clinical symptoms may also be nonspecific. Fatigue, nausea, weakness, or mild confusion can be overlooked or linked to another problem. That is why the anion gap is helpful as a clue in the setting of suspected metabolic acidosis. It can uncover hidden acid gain even when the patient is not obviously unstable.
The anion gap is especially useful because it can show an abnormality before the full clinical picture becomes obvious. In that sense, it works as a practical screening tool for acid-base disorders. When combined with labs and bedside findings, it supports better clinical correlation and improved diagnosis.
Frequent Causes of a High Anion Gap
Various conditions can lead to a high anion gap metabolic acidosis. One major cause is lactic acidosis, in which lactate builds up when tissues do not get enough oxygen or when metabolism is stressed. Another frequent cause is ketoacidosis, which can occur with diabetes, starvation, or heavy alcohol use. Under these conditions, acid production goes up and pushes the gap upward.
Renal failure can also lead to a high anion gap because the kidneys cannot clear acid efficiently. As renal function declines, acids and other retained solutes contribute to the elevation. This renders kidney-related acid-base changes an important part of any serum chemistry review.
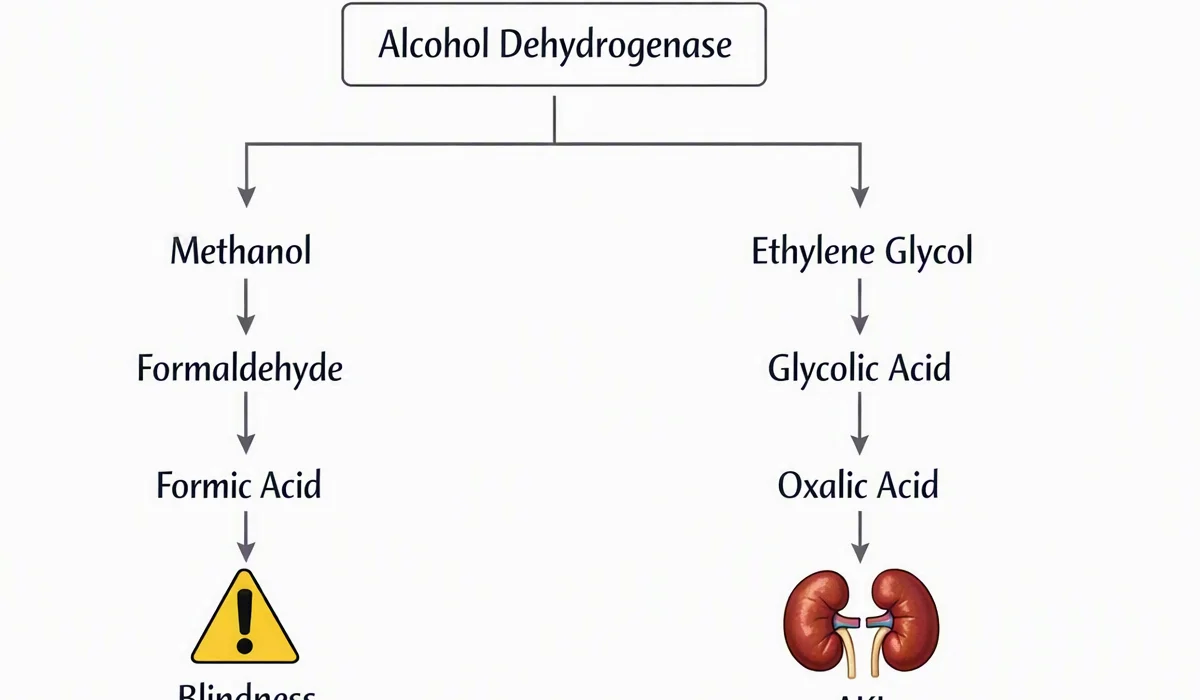
Toxic alcohols are another major cause. Substances such as methanol or ethylene glycol can produce dangerous acid metabolites and lead to a large gap. In certain cases, the osmolar gap may also be elevated, which adds another clue that a toxic ingestion may be involved. Because these causes can be life-threatening, the MUDPILES acronym meaning result should be interpreted rapidly and in context.
Albumin Adjustment and Why It Matters
Hypoalbuminemia can lead to the measured anion gap look falsely normal or only mildly elevated. Since albumin carries a negative charge, lower albumin decreases the baseline gap. That means an significant acid-base problem may be hidden unless a corrected anion gap is calculated.
The idea behind albumin correction is clear: if albumin is low, the reported gap should be adjusted upward to better represent the true acid burden. This improves acid-base interpretation and helps reveal hidden metabolic acidosis. In other words, the corrected value may uncover clinically important unmeasured anions that were not obvious in the raw number.
For this reason, albumin should be considered whenever the anion gap does not align with the clinical picture. A normal-looking result in a patient with low albumin may still mask a real acid-base abnormality. The corrected value provides a more accurate framework for understanding the patient's serum chemistry and overall status.
How Anion Gap Aligns with interpreting blood gases
The gap becomes more revealing when paired with an arterial blood gas. The blood gas gives direct information about pH, PaCO2, and bicarbonate, while the anion gap assists show whether the problem involves acid accumulation. Together, they provide a better picture of the acid-base state.
If the pH is low and bicarbonate is reduced, metabolic acidosis is likely. The PaCO2 can show whether respiratory compensation is occurring, such as through faster breathing to blow off carbon dioxide. If the anion gap is high, that indicates a gap-producing disorder rather than basic bicarbonate loss.
In many cases, the blood gas and anion gap should be read together rather than separately. A patient may have an abnormal gap with only mild changes on the gas, or vice versa. That is why clinical correlation matters: the numbers need to fit the patient's condition, symptoms, and broader diagnostic context.
Limitations of the Calculator
While a well-designed calculator has limits. Test variability can alter the result because different instruments and methods may produce slightly different electrolyte values. Tiny differences in sodium, chloride, or bicarbonate can change the final gap enough to affect assessment.
Analytical error can also be a factor. A single unexpected result may reflect collection or processing issues rather than a true physiologic change. That is why the anion gap should not be used in isolation. It is only one part of the overall evaluation.
The calculator does not replace the broader workup for acid-base problems. The osmol gap, other chemistry values, and clinical findings may be necessary to identify toxic ingestions, kidney problems, or other causes. In the end, the value is best viewed as a valuable clinical aid that still requires careful clinical interpretation.
When to Seek Medical Evaluation
Abnormal anion gap results should be taken seriously when they occur with urgent symptoms. These may include worsening weakness, persistent vomiting, severe dehydration, or signs that the body is struggling to maintain normal acid-base balance. Because the anion gap can be linked to serious disease, prompt evaluation may be necessary.
Confusion and shortness of breath are especially important warning signs. Confusion can reflect worsening acid-base disturbance, poor perfusion, or toxin exposure. Shortness of breath may signal compensatory hyperventilation or another emergency process. In these situations, emergency care is appropriate rather than waiting for repeat testing.
If a person has abnormal lab results along with symptoms, the next step is typically clinician review and additional testing. The anion gap is useful for early detection, but it does not replace medical judgment. Rapid assessment is especially important when toxic alcohols, severe lactic acidosis, or advanced renal failure are possible.
Frequently Asked Questions
What is anion gap calculator used for?
An anion gap calculator is used to efficiently calculate the anion gap from routine lab values and help detecting possible acid base disorders. It is especially helpful for identifying hidden metabolic acidosis, estimating unmeasured acids, and informing further interpretation of lab results. When albumin is included, it can also increase the accuracy of the corrected anion gap.
What is a high anion gap mean in metabolic acidosis?
A high result usually indicates that excess acids are building up in the body, creating high anion gap metabolic acidosis. Common causes include lactic acidosis, ketoacidosis, renal failure, and toxic alcohols. The number is a sign that should be compared with blood gas findings, symptoms, and the rest of the electrolyte data.
How do you correct the anion gap for low albumin?
When hypoalbuminemia is present, the measured gap may be falsely low. A corrected anion gap modifies the result upward to account for reduced albumin. This albumin adjustment helps refine acid-base interpretation and can reveal a hidden gap that was masked by low protein levels.
Is a normal anion gap possible with metabolic acidosis?
Yes. A normal anion gap can still occur in metabolic acidosis, especially when bicarbonate loss is balanced by an increase in chloride. This is often called normal anion gap, or hyperchloremic, metabolic acidosis. That is why the result must be interpreted with the rest of the serum chemistry and not used alone.
Which conditions may cause a low or high anion gap?
A high anion gap can result from lactic acidosis, ketoacidosis, renal failure, or toxic alcohols. A low anion gap may occur with hypoalbuminemia, lab issues, or less common blood chemistry patterns. Because both are influenced by the full electrolyte panel, the result should always be reviewed with clinical correlation.
When should abnormal anion gap results be evaluated urgently?
Urgent evaluation is needed when results are abnormal when they occur with urgent symptoms such as confusion, shortness of breath, severe weakness, or evidence of poisoning. If an abnormal gap appears alongside a low pH, altering PaCO2, or alarming arterial blood gas results, urgent treatment may be needed. The anion gap serves as an important warning sign, but severe symptoms should not ever ignored.