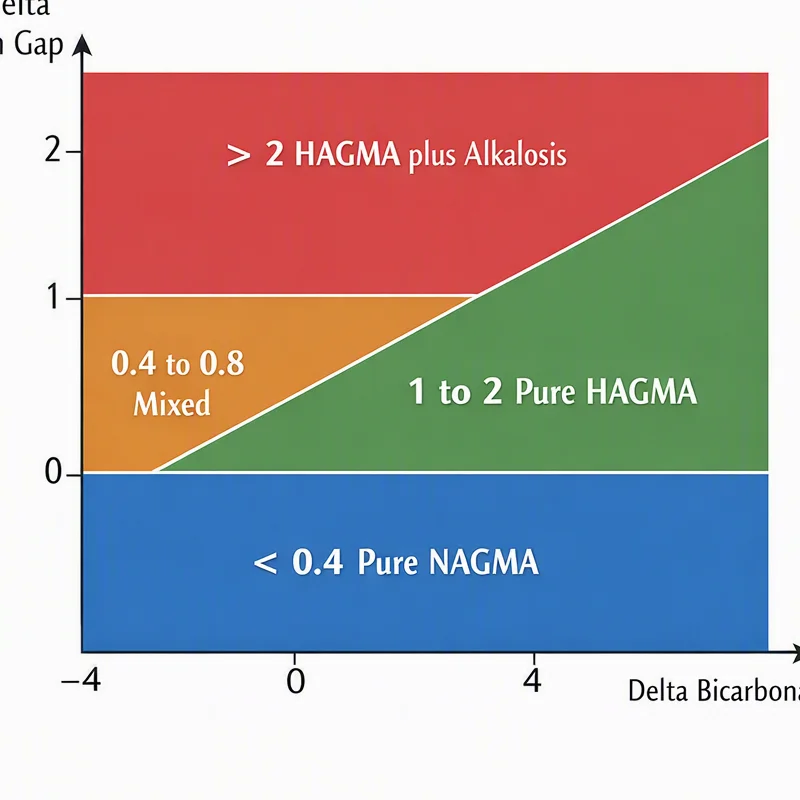
How an anion gap calculator measures
An anion gap calculator is used to estimate the difference between standard measured cations and anions in the blood, usually using sodium, chloride, and bicarbonate. This calculation is a rapid way to check whether there are extra unmeasured anions contributing to an anion gap abnormality. In toxicology, that matters because certain poisons can create a dangerous acid-base disturbance before the cause is obvious.
The most common anion gap formula is:
Anion gap = sodium - (chloride + bicarbonate)
Some clinicians also account for potassium, but the simplified version is used most often in routine electrolyte panel interpretation. The result gives a practical snapshot of serum bicarbonate loss or added acids in the bloodstream. For a patient with suspected poisoning, the calculator is not a diagnosis by itself, but it can rapidly raise or lower clinical suspicion.
Because the gap depends on the measured serum electrolytes, it reflects the current state of the blood chemistry rather than a specific toxin. That is why it should be interpreted alongside symptoms, exposure history, blood gas results, and serum osmolality. In practice, the anion gap is one of the most useful screening tools for identifying a hidden metabolic derangement when the presentation is unclear.
How toxic alcohol ingestion increases the anion gap
Toxic alcohol exposure can produce severe poisoning because the starting alcohol and its metabolites disrupt normal metabolism. The classic agents are methanol and ethylene glycol, though propylene glycol can also contribute in some situations. These substances are toxic not only because of the compounds themselves, but because the body metabolizes them into acidic metabolites that drive acidic buildup.
In methanol exposure, the metabolism generates formic acid, which leads to high anion gap metabolic acidosis AG changes with toxic alcohols and can damage the optic system. That is why vision changes is such an important clue. In ethylene glycol exposure, metabolism creates glycolic acid and other acids that may lead to increasing acidosis and kidney injury.
The anion gap rises because these acidic compounds act as unmeasured anions. As bicarbonate buffers the acid, the serum bicarbonate level falls, and the gap widens. This is why a patient may initially appear relatively stable but then rapidly progress to an anion deficit and severe illness. The pattern is especially important when the history is incomplete and the presentation is only supported by subtle neurologic changes, abdominal symptoms, or unexplained acidosis.
Not every toxic alcohol behaves the same way. Isopropanol, for example, is classically associated with ketosis and central nervous system depression but does not usually cause the same high anion gap pattern because it is metabolized to acetone rather than a strongly acidic metabolite. That distinction is essential for accurate laboratory interpretation and next-step management.
How to work out the anion gap in simple steps
When using an anion gap calculator accurately, start by obtain the most recent lab values from the chemistry results. You will need the measured sodium, chloride, and bicarbonate. These values are typically part of routine serum electrolytes and may be paired with additional toxicology studies, a blood gas, and a measured serum osmolality.
The basic steps are straightforward:
- Identify the sodium value. Identify the chloride value. Note the bicarbonate value. Add chloride and bicarbonate together. Deduct that sum from sodium.
As an example: if sodium is 140, chloride is 100, and bicarbonate is 12, then the anion gap is 28. That is elevated and suggests a high anion gap metabolic acidosis. In the setting of possible poisoning, that number should trigger urgent review of the exposure history and lab context.
One key refinement is the albumin correction. Because albumin is a major unmeasured anion, low albumin can make the measured anion gap look falsely normal or only mildly increased. The albumin-corrected anion gap helps account for that effect and improves diagnostic threshold accuracy. A common clinical approach is to adjust the gap upward when albumin is low so hidden acid accumulation is not missed.
This correction matters because patients with poisoning may also have poor nutrition, chronic illness, or fluid shifts that reduce albumin. Without adjustment, the calculator may underestimate the severity of the metabolic problem. In toxicology, careful use of the formula improves clinical interpretation and prevents false reassurance.
Reading high anion gap results in suspected poisoning
A increased reading on an anion gap calculator does not prove toxic alcohol exposure, but it can strongly support it when matched by the relevant history and symptoms. The main finding is high anion gap metabolic acidosis, which signals too much acids or acid precursors in the bloodstream. In suspected poisoning, that finding should immediately trigger a wider assessment of acid-base status.
One of the best companion tests is the osmolar gap, which measures measured serum osmolality with calculated osmolality. Early in toxic alcohol exposure, the osmolar gap may be increased because the parent alcohol is still present. Later, as metabolism proceeds, the osmolar gap may fall while the anion gap rises. This evolving pattern is a classic clue in toxicology and can help classify the poisoning.
Clinical interpretation depends on timing. A patient who presents early may have a prominent osmolar gap with only mild acidosis. A patient who presents later may show pronounced metabolic acidosis and a substantial anion gap, even if the osmolar gap is no longer impressive. That is why the combination of clinical suspicion, laboratory interpretation, and exposure history counts more than any single value.
The presence of neurologic changes, visual complaints, rapid breathing, or evidence of kidney injury heightens concern for toxic alcohol ingestion. A blood gas can show the severity of acidemia, while serum studies help identify the metabolic derangement. If the pattern fits, urgent treatment should begin before confirmatory toxicology results return.
In suspected poisoning, a normal or borderline anion gap does not safely exclude toxic alcohol ingestion, especially if the patient presented early or has low albumin.
Typical harmful alcohol exposures and their test patterns
Distinct toxic alcohols cause varied patterns, and spotting them can increase the timeliness of care. Methanol poisoning is typically associated with increasing anion gap metabolic acidosis and visual symptoms. Its metabolism creates formic acid, which is directly toxic and contributes to both acidosis and eye injury. A patient may initially have vague symptoms and later develop worsening neurologic symptoms or visual disturbance.
Ethylene glycol poisoning often presents with a comparable high anion gap pattern, but the metabolites are different. Ethylene glycol is converted to glycolic acid and other compounds that worsen acidosis and can damage the kidneys. Crystal formation may also contribute to kidney injury, so renal findings are especially important. In practice, the blood gas, serum electrolytes, and osmolar gap combined help strengthen the case.
Isopropanol is a useful contrast because it usually causes an osmolar gap without the same degree of high anion gap metabolic acidosis. Instead, it may produce ketosis and central nervous system depression. That makes clinical interpretation unlike from methanol or ethylene glycol, even though all are toxic alcohols.
Propylene glycol is another relevant exposure, often associated to certain medications or solvent-containing products. It can contribute to metabolic acidosis and elevated osmolar gap depending on dose and metabolism. Although it is less typical than methanol or ethylene glycol, it belongs in the differential when laboratory patterns do not fit more common causes.
These patterns are not absolute. Timing, coexisting illness, and treatment can change the picture. Still, matching the lab pattern to the likely alcohol can make toxicology evaluation more targeted and can guide urgent treatment decisions.
Constraints of the anion gap calculator
The anion gap calculator is helpful, but it has significant constraints. First, albumin changes the starting point. Low albumin can lower the measured gap and hide significant acid buildup, which is why the albumin-corrected anion gap is often more reliable in ill patients.
In addition, many other conditions can also cause a high gap. Lactic acidosis can increase the gap in shock, hypoxia, seizures, or severe infection. Ketoacidosis from diabetes, starvation, or alcohol use can result in a similar pattern. Renal failure can cause retention of acids and unmeasured anions as kidney clearance declines. These are frequent alternative explanations that must be considered before labeling the problem as toxic alcohol ingestion.
Also, timing matters. A patient may present before enough metabolite has formed to elevate the gap. Another patient may present after the parent alcohol has already been metabolized, leaving a severe high anion gap but little or no osmolar gap. This makes serial assessment critical, especially when the exposure history is unclear.
Finally, the gap is only one piece of the puzzle. A blood gas, serum osmolality, renal function tests, and toxicology consultation may all be needed for a confident diagnosis. The calculator supports decision-making, but it does not replace full laboratory interpretation and bedside assessment.
When to seek immediate medical evaluation
Possible toxic alcohol ingestion is a serious emergency. If there is a credible exposure history, unexplained metabolic acidosis, or symptoms such as confusion, visual disturbance, severe vomiting, rapid breathing, or altered mental status, prompt evaluation is needed. Do not hold off for symptoms to worsen.
Call poison control immediately for expert guidance. They can help interpret the likely toxicology pattern and advise on next steps based on the substance, timing, and available labs. In parallel, the patient should be evaluated in the emergency department, where rapid lab testing and treatment can start.
Specific treatments may include an antidote such as fomepizole or, in some settings, ethanol-based anion gap clinical significance therapy, depending on clinical circumstances and local protocols. If the poisoning is severe, or if there is significant acidosis, end-organ injury, or high toxin burden, hemodialysis may be needed to remove the alcohol and its toxic metabolites.
Urgent treatment is especially important when there are neurologic symptoms, worsening kidney injury, or a rapidly rising anion gap. The earlier therapy begins, the better the chance of preventing permanent injury. In toxic alcohol cases, waiting for confirmatory testing can be dangerous.
Common questions about anion gap and toxic alcohols
What does a anion gap calculator show in suspected toxic alcohol ingestion?
An anion gap tool estimates whether there is a gap between measured cations and anions, using sodium, chloride, and bicarbonate. In suspected toxic alcohol ingestion, a high result suggests extra unmeasured anions from toxic metabolites and supports concern for high anion gap metabolic acidosis. It is most useful when combined with the osmolar gap, blood gas, and exposure history.
How is the anion gap calculated from sodium, chloride, and bicarbonate?
The standard anion gap formula is sodium minus the sum of chloride and bicarbonate. If sodium is 138, chloride is 102, and bicarbonate is 14, the anion gap is 22. Many clinicians also apply an albumin correction when albumin is low so the result better reflects actual acid-base status.
What is the difference between anion gap and osmolar gap?
The anion gap reflects unmeasured anions in the blood, while the osmolar gap reflects unmeasured osmotically active substances in serum osmolality. In toxic alcohols, the osmolar gap may be high early because the parent alcohol is present, while the anion gap rises later as acidic metabolites accumulate. Both are important in clinical interpretation.
Can a normal anion gap rule out methanol or ethylene glycol poisoning?
No. A normal anion gap does not rule out methanol or ethylene glycol poisoning, especially early after exposure or when albumin is low. The osmolar gap, blood gas, and clinical suspicion may still support toxic alcohol ingestion before the anion gap becomes elevated. Serial testing is often necessary.
When does someone with suspected toxic alcohol ingestion seek emergency care?
Emergency care is needed right away if there is suspected exposure plus symptoms such as confusion, visual disturbance, severe vomiting, rapid breathing, or collapse. Contact poison control and go to the emergency department without delay. Severe cases may require an antidote and hemodialysis to prevent worsening metabolic acidosis and organ damage.